Skip to content

Our Insights

Designed by physicians for physicians, eNavvi empowers prescribers with the autonomy to practice anytime, anywhere, simplifying your practice and enhancing decision-making efficiency.

E-Prescribing for Dentists: What a Small Dental Practice Actually Needs, and What It Can Skip

Dentists are a distinct case in e-prescribing. Most dental prescriptions are short courses of antibiotics, NSAIDs, and a few other non-controlled medications. Opioid prescribing by dentists has fallen sharply, and the profession's own guideline now puts NSAIDs first for acute dental pain. Yet state e-prescribing mandates for controlled substances apply to dentists just as they do to physicians, and the practice-management software many dental offices run either lacks an e-prescribing module or prices one for a much larger practice.

This article covers what a small dental practice needs from e-prescribing software, how state mandates and low-volume exemptions generally apply to dentists, what dental-oriented e-prescribing costs, and how a standalone tool such as eNavvi fits alongside a dental practice-management system.

This is general information about regulations and software, not legal or clinical advice. Requirements vary by state and change over time, so confirm current rules with your state dental board.

The short answer

A dental practice needs an e-prescribing tool that connects to Surescripts for ordinary prescriptions, supports DEA-compliant EPCS for occasional Schedule II–IV prescriptions where your state requires it, accepts DDS and DMD prescribers, and doesn’t charge a full medical-EHR price for a practice that writes a handful of prescriptions a day. Whether it must integrate with your practice-management system depends on how much you value the prescription appearing in the chart automatically versus paying for the integration.

What dentists actually prescribe

Dental prescribing is low-volume and concentrated in a few categories. The controlled-substance share has been shrinking. In a JADA analysis of IQVIA prescription data covering 2015 to 2019, opioid prescriptions by U.S. dentists fell 34.4% overall; 14.8% of dentists wrote no opioid prescriptions, 46.0% were low prescribers, and 3.4% were consistently high prescribers (JADA, November 2023).

The American Dental Association's 2024 clinical practice guideline recommends NSAIDs, alone or with acetaminophen, as first-line treatment for acute dental pain in adults and adolescents 12 and older, and reserves opioids for limited circumstances with shared decision-making and attention to storage and disposal (ADA News, February 5, 2024). ADA policy since 2018 has also supported statutory limits of no more than seven days for opioids prescribed for acute pain (ADA, 2018).

The consequence for software selection: most dentists need EPCS rarely, but when they need it, they need it to work, and the state may require it. A tool that charges by prescription volume or bundles EPCS into an expensive medical EHR is a poor fit for this profile.

Do state e-prescribing mandates apply to dentists?

Generally yes. Many states require electronic prescribing of controlled substances, and those requirements apply to dentists as they do to physicians, with state dental boards typically responsible for enforcement. Most of these states also provide exemptions or waivers, and the details vary: some exempt prescribers who issue fewer than a set number of prescriptions a year, some grant time-limited waivers on application to the dental board or another agency, and some require exempt prescribers to register annually and continue using tamper-resistant paper. Your state dental board's website is the authoritative source for what applies to you.

Separately, the federal CMS EPCS Program requires prescribers to e-prescribe at least 70% of Schedule II–V controlled-substance prescriptions for Medicare Part D patients, with an automatic exception for prescribers who issue 100 or fewer qualifying Part D controlled-substance prescriptions in a year (CMS EPCS Program). A dentist whose Part D controlled-substance prescriptions stay at or below that number qualifies for the exception automatically, but the program applies to any prescriber whose prescriptions are filled under Part D, and it is separate from state requirements.

The practical reading: count your controlled-substance prescriptions for the last twelve months. If the number qualifies you for a state exemption, you have a choice. If it does not, or your state has no low-volume exemption, you need EPCS. An exemption that requires annual paperwork, paper prescriptions, and manual processes may cost more in staff time than a low-cost EPCS subscription, so compare both paths rather than assuming the exemption is cheaper.

Integrated module or standalone tool

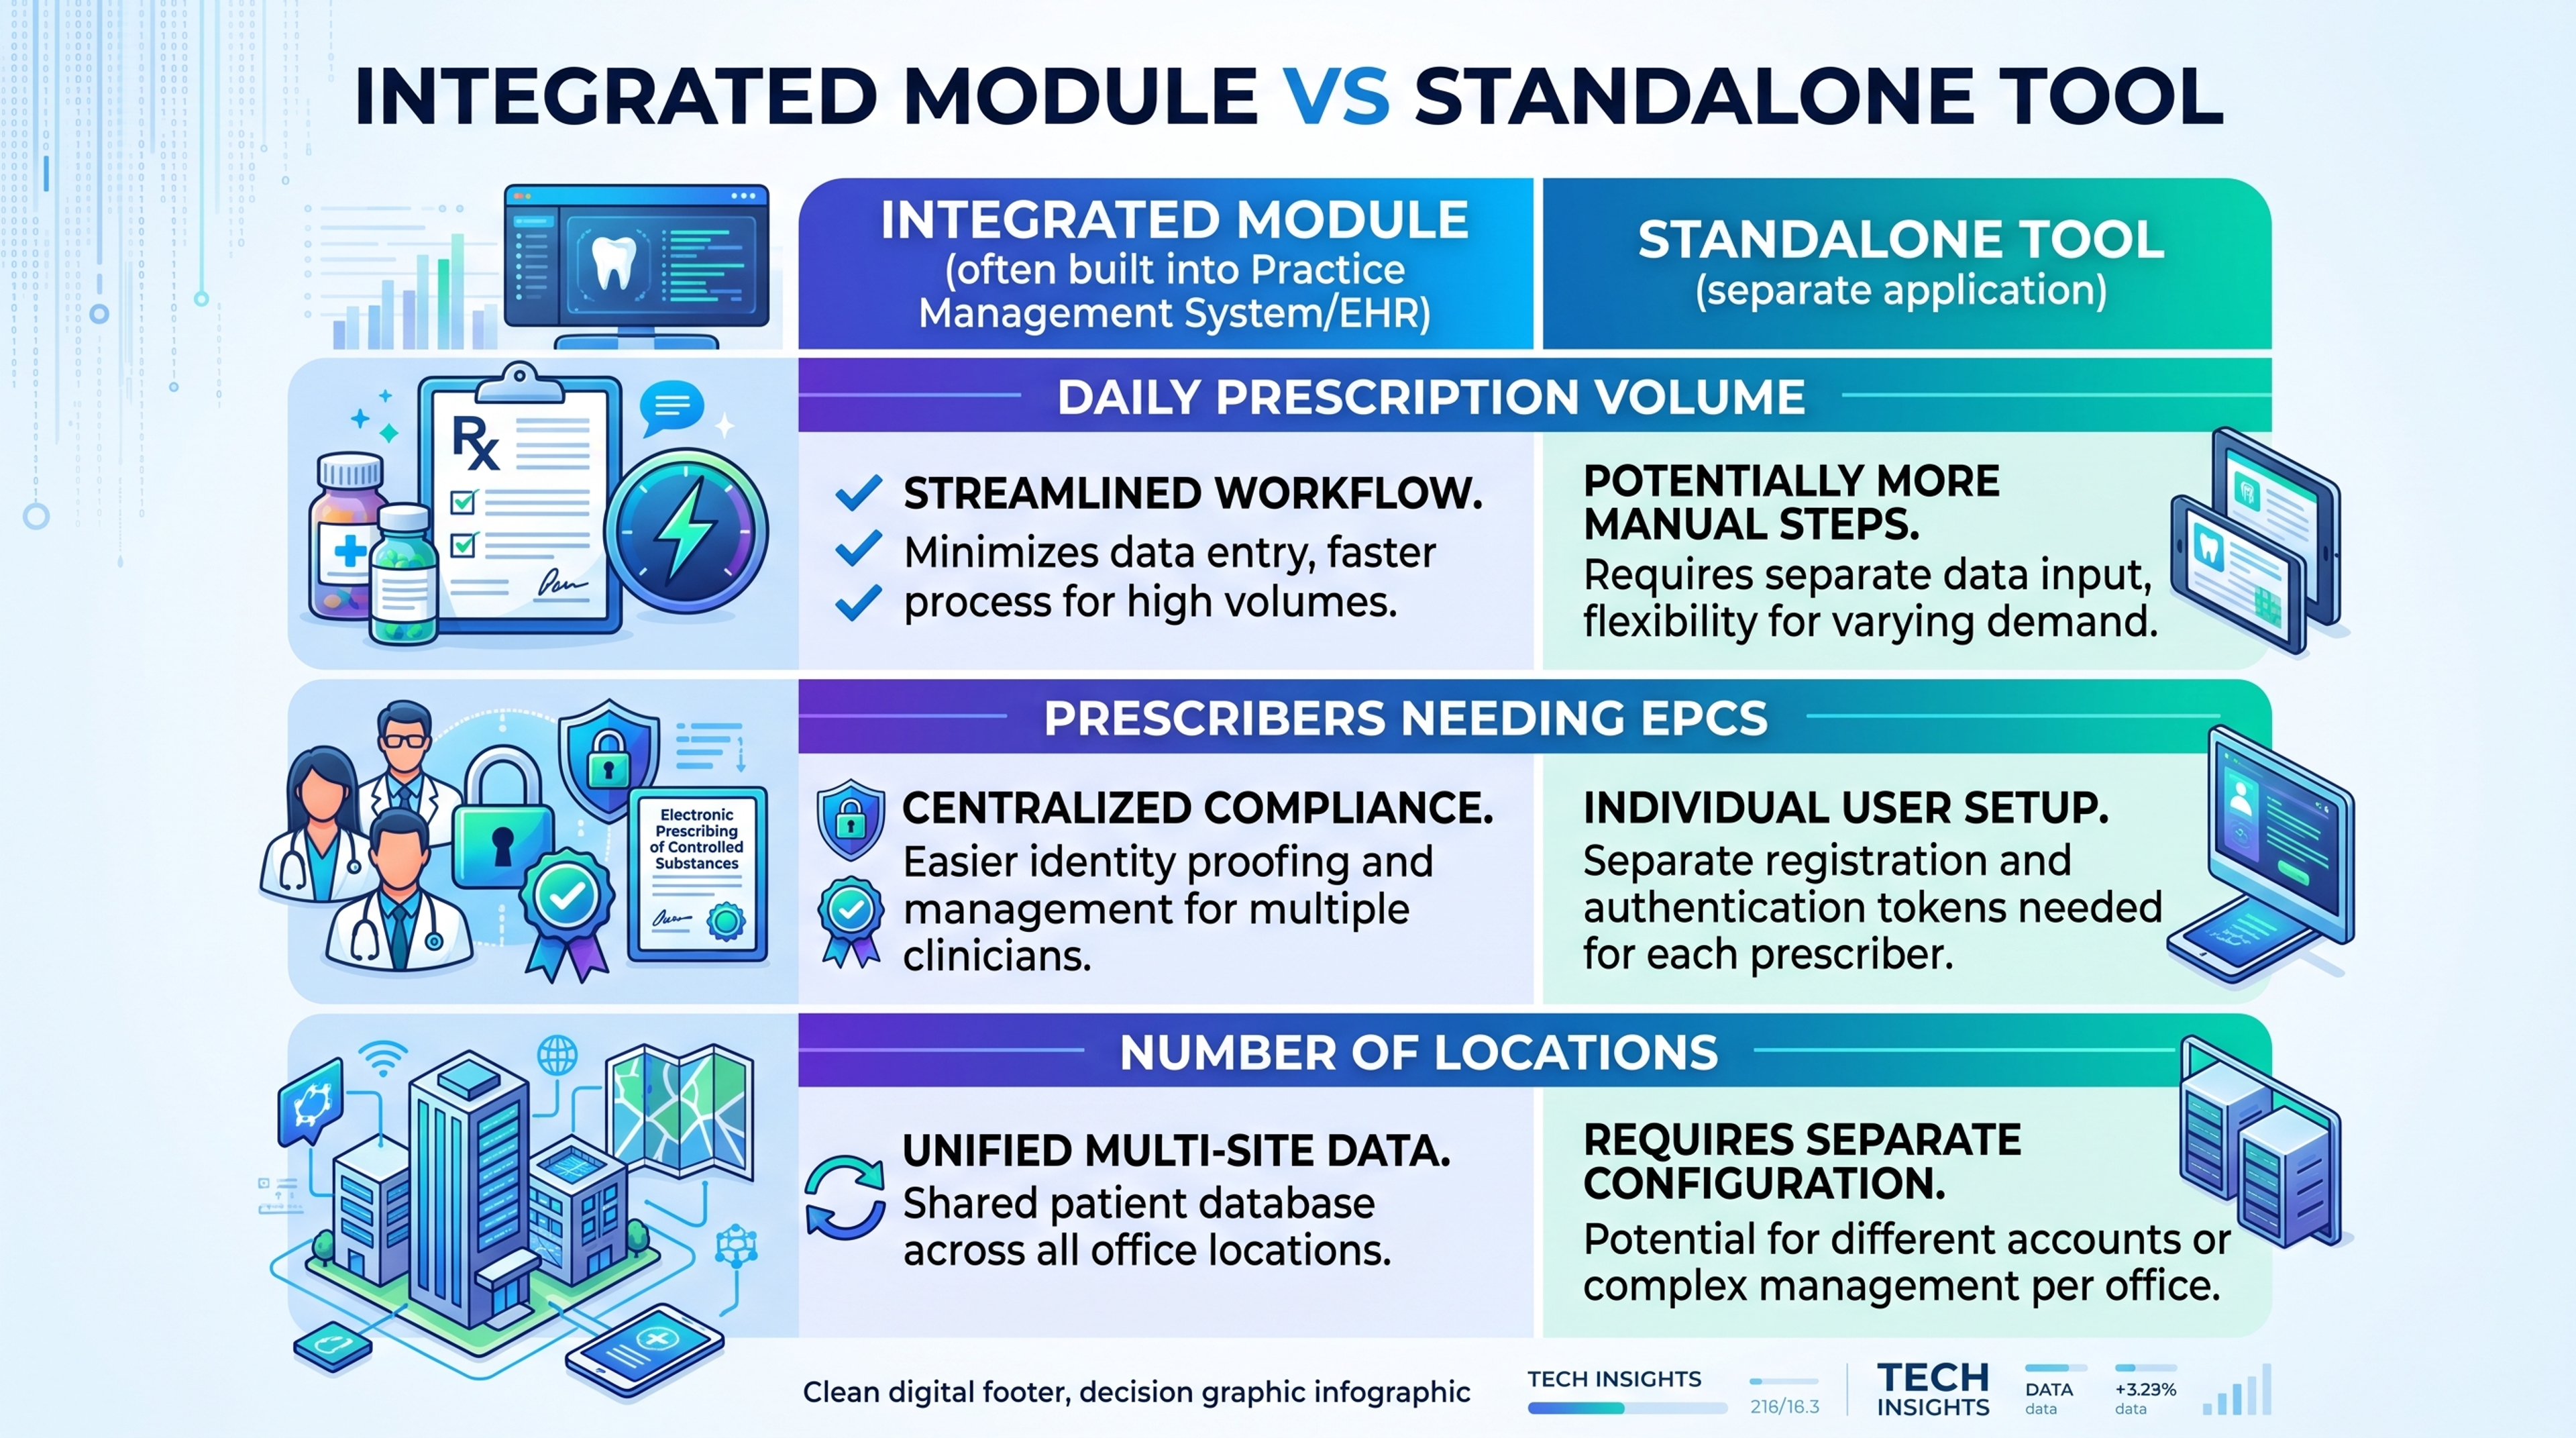
Dental practice-management systems such as Dentrix and Eaglesoft offer e-prescribing modules from their vendors. The advantage is that the prescription is written from the patient's chart and recorded there. The costs are less visible: the vendor pages checked for this article did not publish a monthly price for the module, and dental-association member offers describe their prices as discounts from a higher regular price.

A standalone tool works from a browser or app independent of the practice-management system. The tradeoff is documentation: you or your staff note the prescription in the chart rather than having it written there. For a practice writing a few prescriptions a day, that is a small habit. For a multi-dentist practice writing dozens, integration may be worth paying for.

Three questions settle it for most practices:

How many prescriptions a day does the whole practice write? Under about ten, standalone documentation is manageable. Above that, price the integration.

How many prescribers need EPCS? Every dentist who signs controlled prescriptions needs their own identity proofing and two-factor credential. Per-prescriber pricing multiplies quickly, so compare on total practice cost, not the headline number.

Do you prescribe from more than one location or from home? Browser-based standalone tools travel; some integrated modules are tied to the office installation.

What dental e-prescribing costs

The table records what each vendor's public page stated when checked on September 24, 2026, or on the date noted. It is a snapshot, not a ranking. Prices, plan contents, and trial terms change, so confirm with each vendor before deciding. Association member pricing is shown where that is the only published figure. Product names belong to their respective owners.
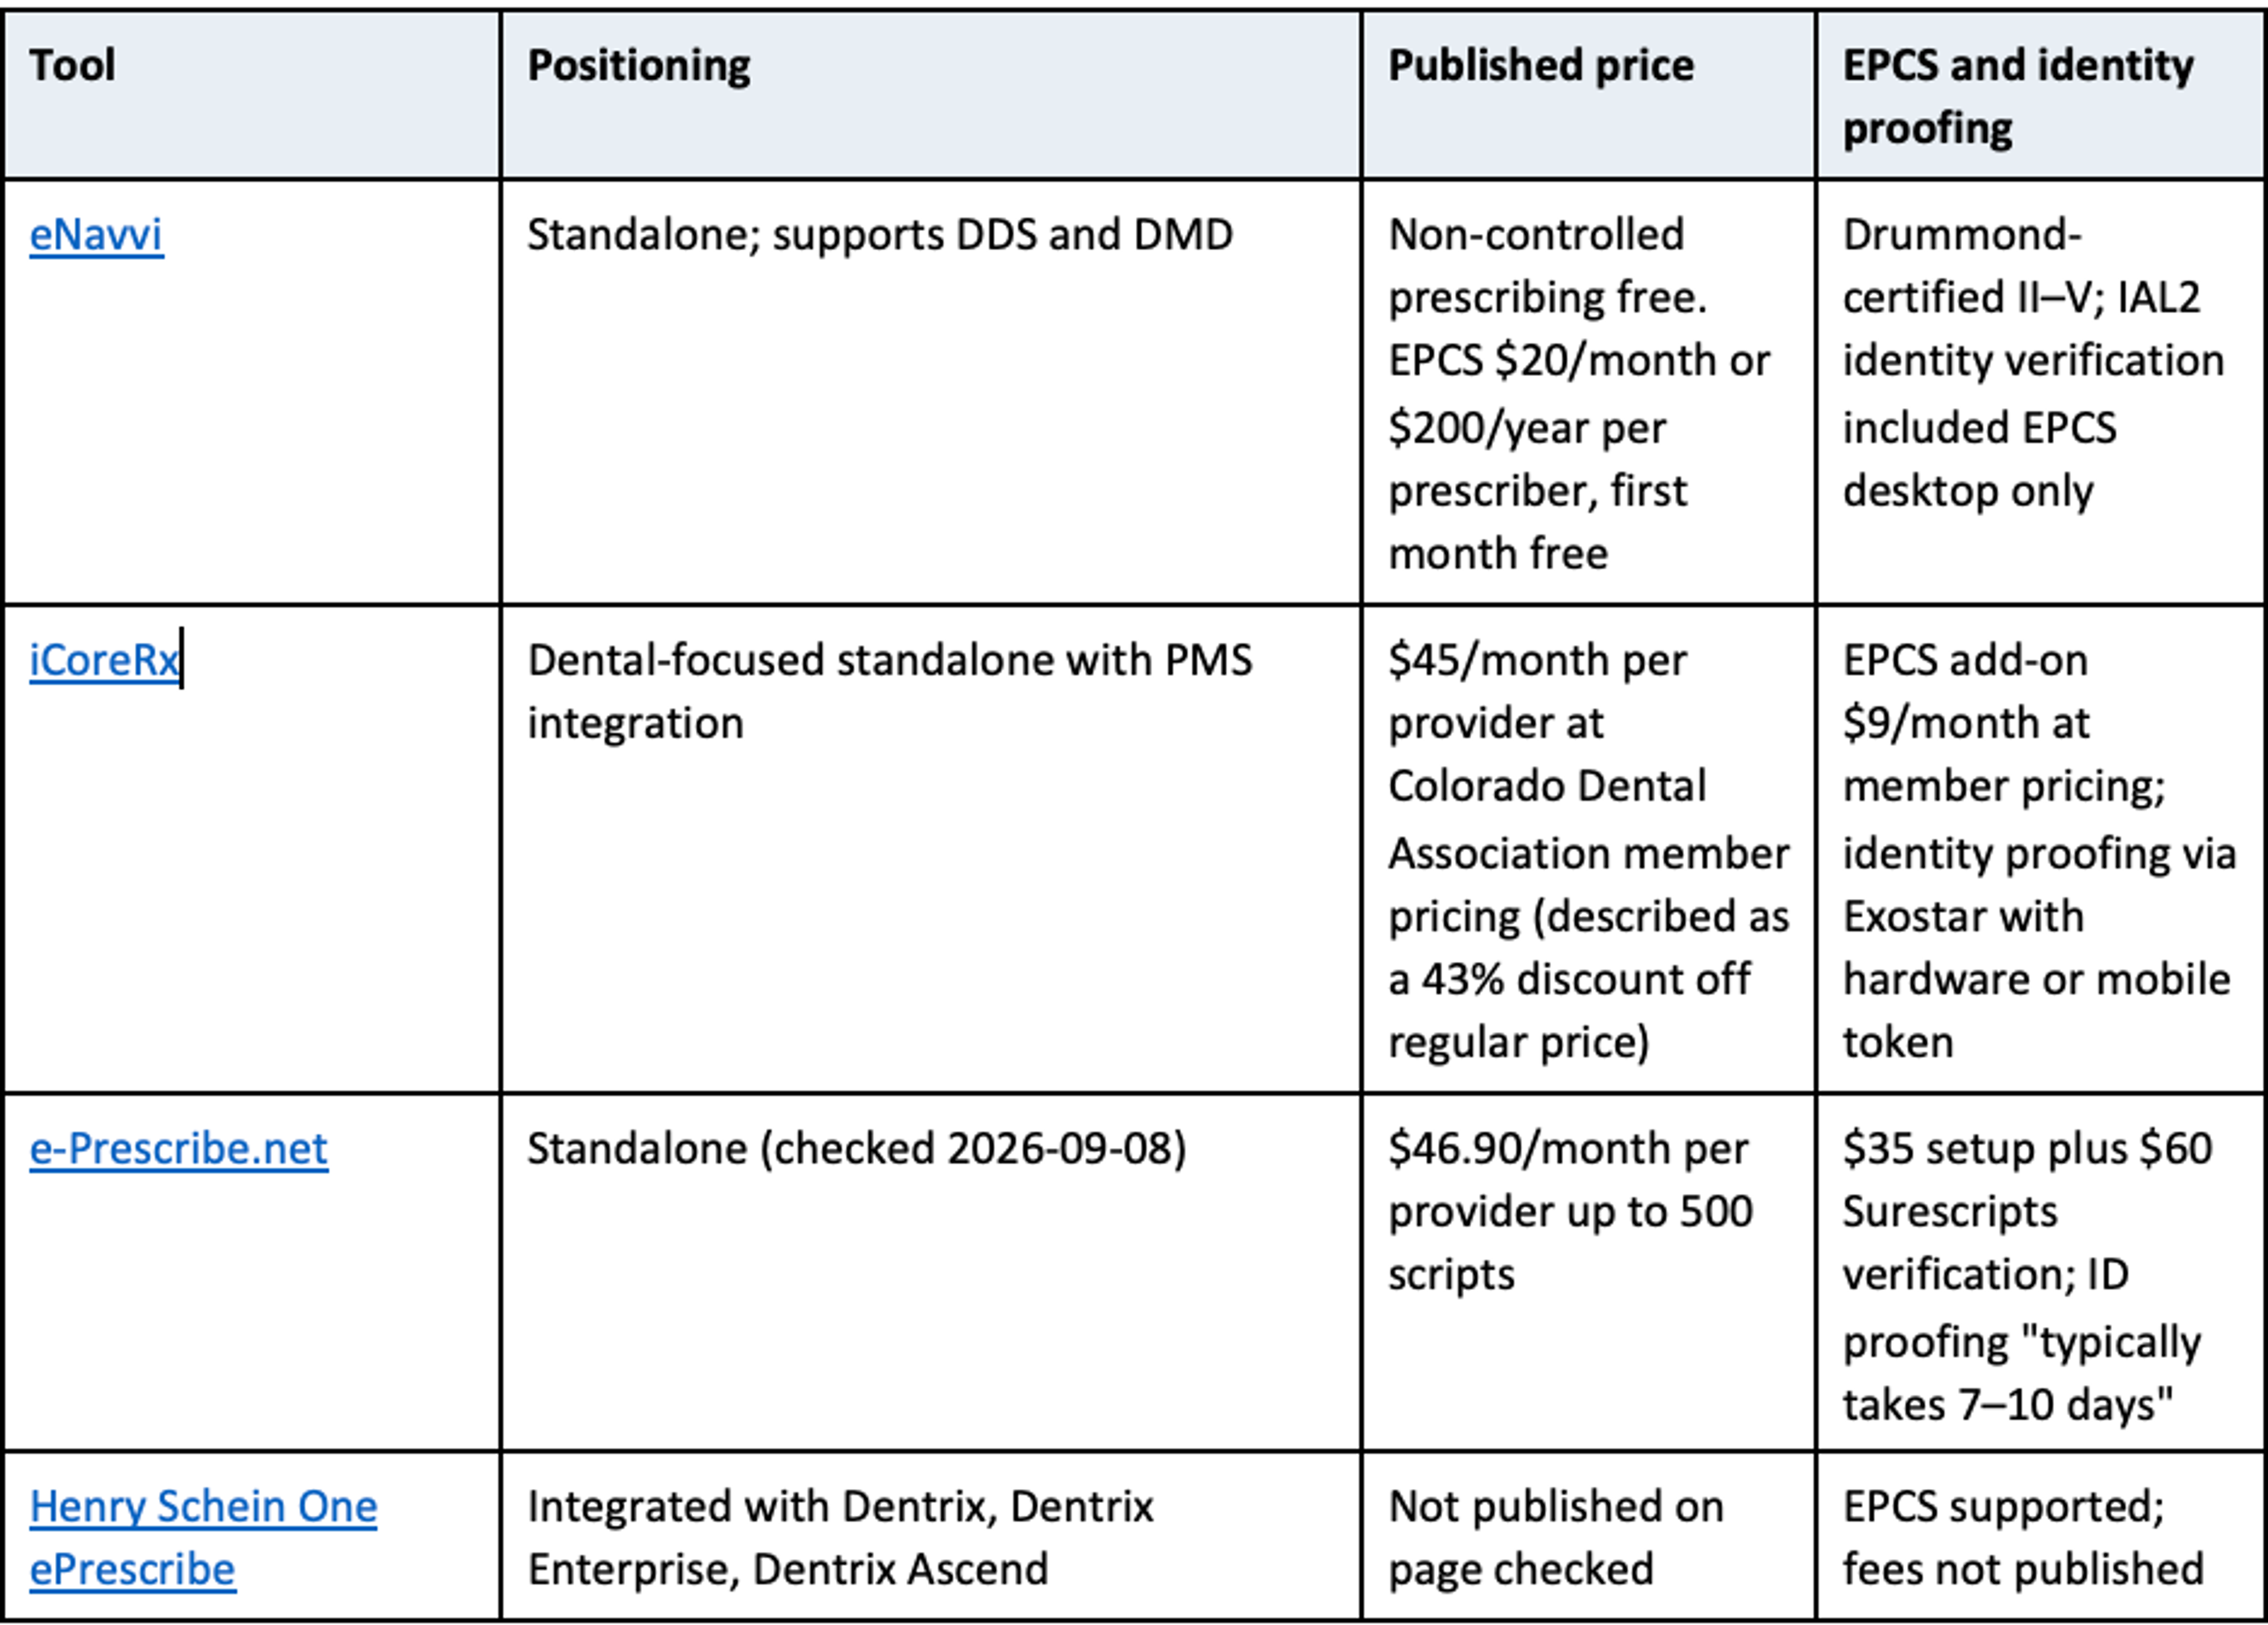
For a solo dentist who writes controlled prescriptions a few times a month, the twelve-month cost on published prices ranges from $200 to roughly $650 depending on the tool, before any practice-management integration fees. For a dentist who never prescribes controlled substances, at least one of these options is free.

A chairside workflow that fits dental practice

The steps below describe how e-prescribing software fits a dental visit. They are not clinical guidance and do not establish a standard of care; prescribing decisions remain yours.

Post-operative prescriptions. Write the NSAID or antibiotic while the patient is still in the chair, choose the pharmacy the patient names, and send it electronically. If the tool shows pharmacy prices, you can tell the patient roughly what a generic will cost before they leave. Cash prices for common generics can vary between nearby pharmacies, so the number is worth a sentence even when the drug is inexpensive. Present it as an estimate, since a quoted price depends on the pharmacy, quantity, and moment of the quote, and the patient's insurance price may differ. The patient chooses the pharmacy.

Antibiotic prophylaxis for a future appointment. Send the prescription with the pharmacy and the appointment date in mind so the patient has it filled before the visit. A tool with saved patient profiles and favorite prescriptions cuts this to seconds on the second visit.

The occasional controlled substance. Check the PDMP as your state requires, prescribe according to your judgment and any state limits on quantity or duration, and sign with two-factor authentication. If you use a standalone tool, note the prescription in the dental chart. Because EPCS on some tools, including eNavvi, is desktop only, keep a desktop or laptop available in the clinical area for these.

Associates and staff. Only a licensed prescriber may issue a prescription. Staff can prepare one for the dentist to review, but each dentist must have their own EPCS credential, may not share it, and must sign controlled-substance prescriptions personally (21 CFR 1311.102). Set user roles accordingly.

Where eNavvi fits for a dental practice

eNavvi is a standalone e-prescribing platform that runs from a browser or mobile app. The Core plan is free and covers unlimited non-controlled prescribing with real-time pharmacy price comparison. The EPCS plan costs $20 per month or $200 per year per prescriber after a one-month free trial, is Drummond-certified for Schedules II–V, includes IAL2 identity verification, and uses Microsoft Authenticator for two-factor signing (eNavvi pricing). eNavvi accepts DDS and DMD prescribers and states that EPCS is available in every state (eNavvi FAQ).

What it does not do: the Core and EPCS plans are standalone, so prescriptions are documented in your chart by hand; like most e-prescribing tools, it does not replace your state PDMP check; and EPCS is desktop only. For a small practice whose controlled-substance volume is low and whose main need is fast, inexpensive, compliant prescribing, those are usually acceptable limits. For a group practice that wants prescriptions written into the chart automatically, eNavvi's Enterprise plan lists EHR and practice-system integration at custom pricing. As with any EPCS vendor, you may ask eNavvi for its current third-party audit or certification report under 21 CFR 1311.300 before relying on the application.

For the general rules behind EPCS, see EPCS Without the EHR: A Guide for Small Dental and Psychiatric Practices.

Questions dentists ask

I only prescribe an opioid a few times a year. Do I still need EPCS? It depends on your state. Some states offer low-volume exemptions or waivers, usually with annual paperwork and continued paper-prescription requirements. Others do not. Check your state dental board, and weigh the cost of maintaining an exemption against a low-cost EPCS subscription.

Can my front-desk staff send prescriptions for me? Staff may prepare a prescription for you to review, but you must review and sign it, and for controlled substances you must sign with your own two-factor credential, which may not be shared.

Does e-prescribing software check the PDMP for me? Some tools offer a PDMP module; many do not. In either case, the legal duty to check at the intervals your state sets remains yours.

Do I need a full medical EHR to e-prescribe? No. Standalone e-prescribing tools work independently of any EHR or practice-management system. The DEA requirements for EPCS concern identity proofing, two-factor authentication, and certified software, not the presence of an EHR.

Next step

If your practice-management system does not include e-prescribing, or prices it for a practice larger than yours, eNavvi's Core plan is free for non-controlled prescriptions and EPCS is $20 a month per dentist. Details are on the pricing page, and you can register at enavvi.com.
Read More
E-Prescribing for Solo Psychiatry and Psychiatric NP Practices: Stimulants, Benzodiazepines, and EPCS Without an EHR

If you run a small psychiatry or psychiatric nurse practitioner (PMHNP) practice, your prescribing needs differ from most other outpatient specialties in one way: controlled substances are often routine maintenance medications, not occasional exceptions. Most stimulants prescribed for ADHD are Schedule II. Benzodiazepines and many hypnotics are Schedule IV. Buprenorphine is Schedule III. A tool that handles non-controlled prescribing well but treats electronic prescribing of controlled substances (EPCS) as an afterthought will cost you time every week.

This article explains what a solo psychiatrist or PMHNP should look for in an e-prescribing tool, the federal rules that shape the stimulant and benzodiazepine workflow, what changes when you prescribe by telehealth, what EPCS costs on platforms small psychiatric practices commonly consider, and where a standalone tool like eNavvi fits.

This is general information about regulations and software, not legal or clinical advice. Requirements vary by state and change over time, so confirm current rules with your state licensing board.

The short answer

A small psychiatric practice needs four things from prescribing software: DEA-compliant EPCS for Schedules II–V, a workflow that handles Schedule II prescriptions without refills, a way to see medication cost before the patient reaches the pharmacy, and pricing that does not force you to buy a full electronic health record (EHR) just to prescribe. A standalone tool can provide all four, but verify each one rather than assume.

Why psychiatry's prescribing workflow is different

Three federal rules shape most of the difference. State law adds requirements on top of each.

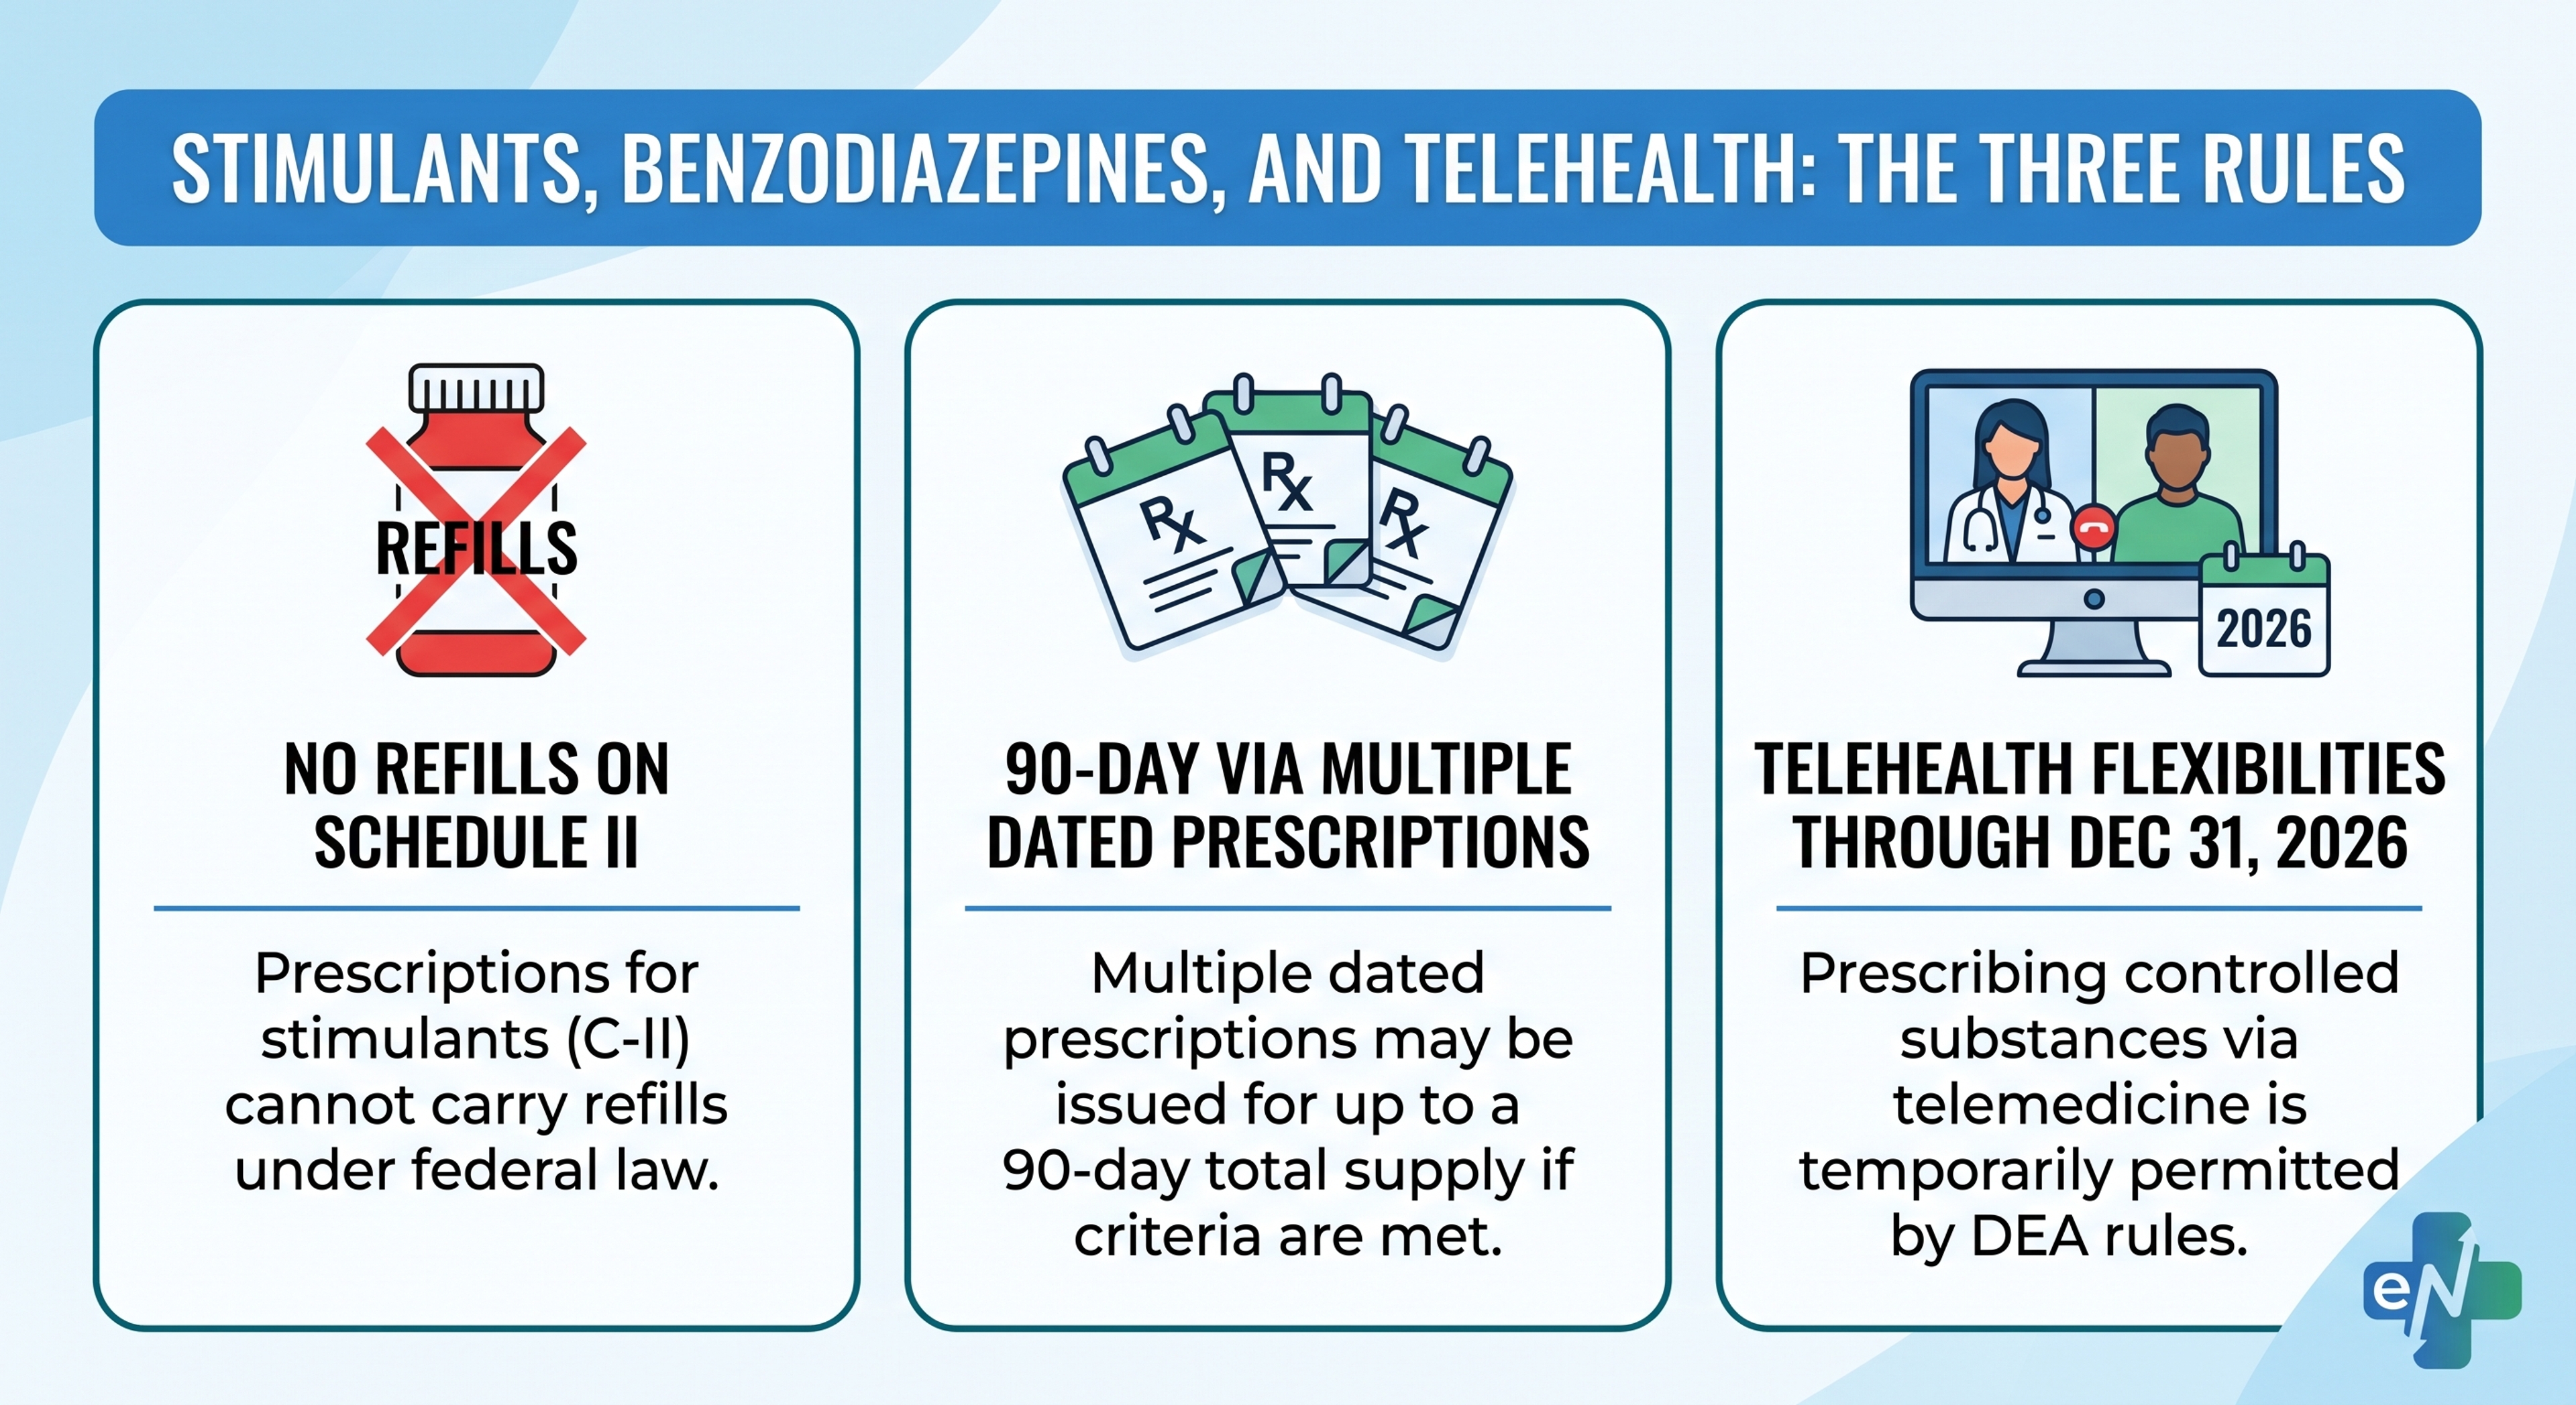
Schedule II prescriptions cannot be refilled. Under 21 CFR 1306.12(a), refilling a Schedule II prescription is prohibited. Every month of a stimulant is a new prescription, individually signed with two-factor authentication. Under 21 CFR 1306.12(b), a practitioner may issue multiple Schedule II prescriptions authorizing up to a 90-day total supply, but only if all of the following are met: each prescription is issued for a legitimate medical purpose by a practitioner acting in the usual course of professional practice; each prescription after the first carries written instructions stating the earliest date a pharmacy may fill it; the practitioner concludes that issuing multiple prescriptions does not create an undue risk of diversion or abuse; and the practice is permitted under applicable state law (21 CFR 1306.12). DEA has also stated that nothing in the rule requires a practitioner to issue multiple prescriptions or to see patients less often than sound medical judgment supports. Your software must support an earliest-fill-date instruction on each electronic prescription for this option to be usable at all.

Schedule III and IV prescriptions may be refilled, within limits. A Schedule III or IV prescription may be refilled no more than five times and may not be filled or refilled more than six months after the date it was issued; beyond that, a new prescription is required (21 CFR 1306.22). State law may be stricter.

EPCS requires identity proofing, two-factor signing, and personal accountability. DEA's rules require each prescriber to be identity-proofed by an approved credential service provider and to sign every controlled-substance prescription using two of three factors: something you know, something you have, or something you are (21 CFR 1311.115; DEA EPCS Q&A). The credential is personal: it may not be shared, a lost or compromised credential must be reported promptly, and the prescriber carries the same responsibility for an electronic prescription as for a paper one (21 CFR 1311.102). Staff may prepare a prescription, but only the prescriber may sign it. For a psychiatrist who signs controlled prescriptions many times a day, the speed of that second factor matters; an authenticator app on your phone is typically faster than a hardware token you have to locate.

Telehealth prescribing of controlled substances runs on temporary federal rules. Since 2020, DEA has allowed practitioners to prescribe controlled substances to patients seen by telemedicine under temporary flexibilities that it has extended several times, most recently through December 31, 2026, while it works on a permanent rule (Holland & Knight summary, January 13, 2026). State telehealth and prescribing laws apply separately and can be stricter. If your practice is telepsychiatry-based, check DEA's current telemedicine guidance and your state's rules before relying on telehealth prescribing, and check again before 2027.

Two state-level obligations sit on top of these. Most states require checking the prescription drug monitoring program (PDMP) before prescribing controlled substances, at intervals that vary by state. Many states also mandate EPCS for controlled substances, with their own exemptions. Neither is handled by the DEA rule, and neither is handled automatically by your prescribing software.

What a psychiatric NP needs to check first

For PMHNPs, the software question comes after the authority question. DEA classifies nurse practitioners as mid-level practitioners, and it states that a mid-level practitioner's authority to prescribe controlled substances, including which schedules, is determined by the state where they practice (DEA Diversion Control, Mid-Level Practitioners). A DEA registration does not expand what the state has granted.

As of May 2026, the American Association of Nurse Practitioners counts 27 states plus Washington, D.C. as full-practice environments, where NPs may prescribe medications and controlled substances under the exclusive licensure authority of the state board of nursing. Reduced- and restricted-practice states require a collaborative agreement, supervision, or delegation for at least one element of practice (AANP State Practice Environment, May 2026). Some states also limit which schedules an NP may prescribe, require additional registration, or require that a collaborative agreement specifically address controlled substances.

Before evaluating any tool, confirm with your state board of nursing that you hold controlled-substance prescriptive authority for the schedules you need, that any required collaborative or supervisory agreement is in place and covers controlled substances, and that your DEA registration is active and lists the correct practice location. Then confirm that the software accepts NPs as prescribers. Not every standalone tool does.

A workflow for stimulants and benzodiazepines

The steps below assume EPCS is already active. They describe how the software workflow can fit the rules above. They are not clinical guidance, do not establish a standard of care, and do not substitute for your own judgment or your state's requirements.

Stimulant renewals. For a patient you see monthly, each visit produces one Schedule II prescription. For a patient you see less often, federal rules permit up to three dated prescriptions totaling no more than a 90-day supply if the conditions in 21 CFR 1306.12(b) are met and your state allows it; some states limit or prohibit the practice. Whichever cadence you use, each prescription is dated on the day it is issued, signed individually with two-factor authentication, and preceded by a PDMP check at the interval your state requires. Document the check.

Supply-constrained stimulants. Methylphenidate extended-release and amphetamine mixed salts have appeared on federal or ASHP shortage lists at various points since 2022, and availability in 2026 still varies by manufacturer and dose (FDA Drug Shortages: methylphenidate ER). A prescription sent to a pharmacy that cannot fill it costs everyone time. Two options exist when that happens. Since August 28, 2023, DEA rules allow a pharmacy, at the patient's request, to transfer an unfilled electronic Schedule II–V prescription one time to another pharmacy for initial filling, pharmacist to pharmacist, without a new prescription (DEA, September 2023). Alternatively, the prescriber can cancel the original electronically (CancelRx) and issue a new one to a different pharmacy. If you reissue, cancel first, so the patient does not hold two active Schedule II prescriptions for the same medication. The choice of pharmacy remains the patient's.

Benzodiazepine tapers. Schedule IV prescriptions may carry up to five refills within six months under federal rules, but a taper is often written as a sequence of decreasing prescriptions rather than as a refillable one. A tool that lets you copy a prior prescription and edit the dose saves more time here than most features shown on a demo. Some states impose additional limits on benzodiazepine prescribing or co-prescribing with opioids; check yours.

The cost conversation. In the most-cited national data, 55.3% of office-based psychiatrists accepted private non-capitated insurance, compared with 88.7% of other office-based specialists, and more than half of office-based psychiatrists were in solo practice (Bishop et al., JAMA Psychiatry 2014, via PMC). That data is from 2009–2010, and a self-pay visit does not mean the patient lacks drug coverage. It does mean a cash-pay practice has no real-time benefit check running through a payer contract. Seeing pharmacy cash prices at the point of prescribing gives those patients a number to compare against their plan's price. Present any quoted price as an estimate: it depends on the pharmacy, the form, the quantity, and the moment of the quote, and the patient's insurance price may differ. The patient chooses the pharmacy; the price information is there to inform that choice.

What EPCS costs a small psychiatric practice

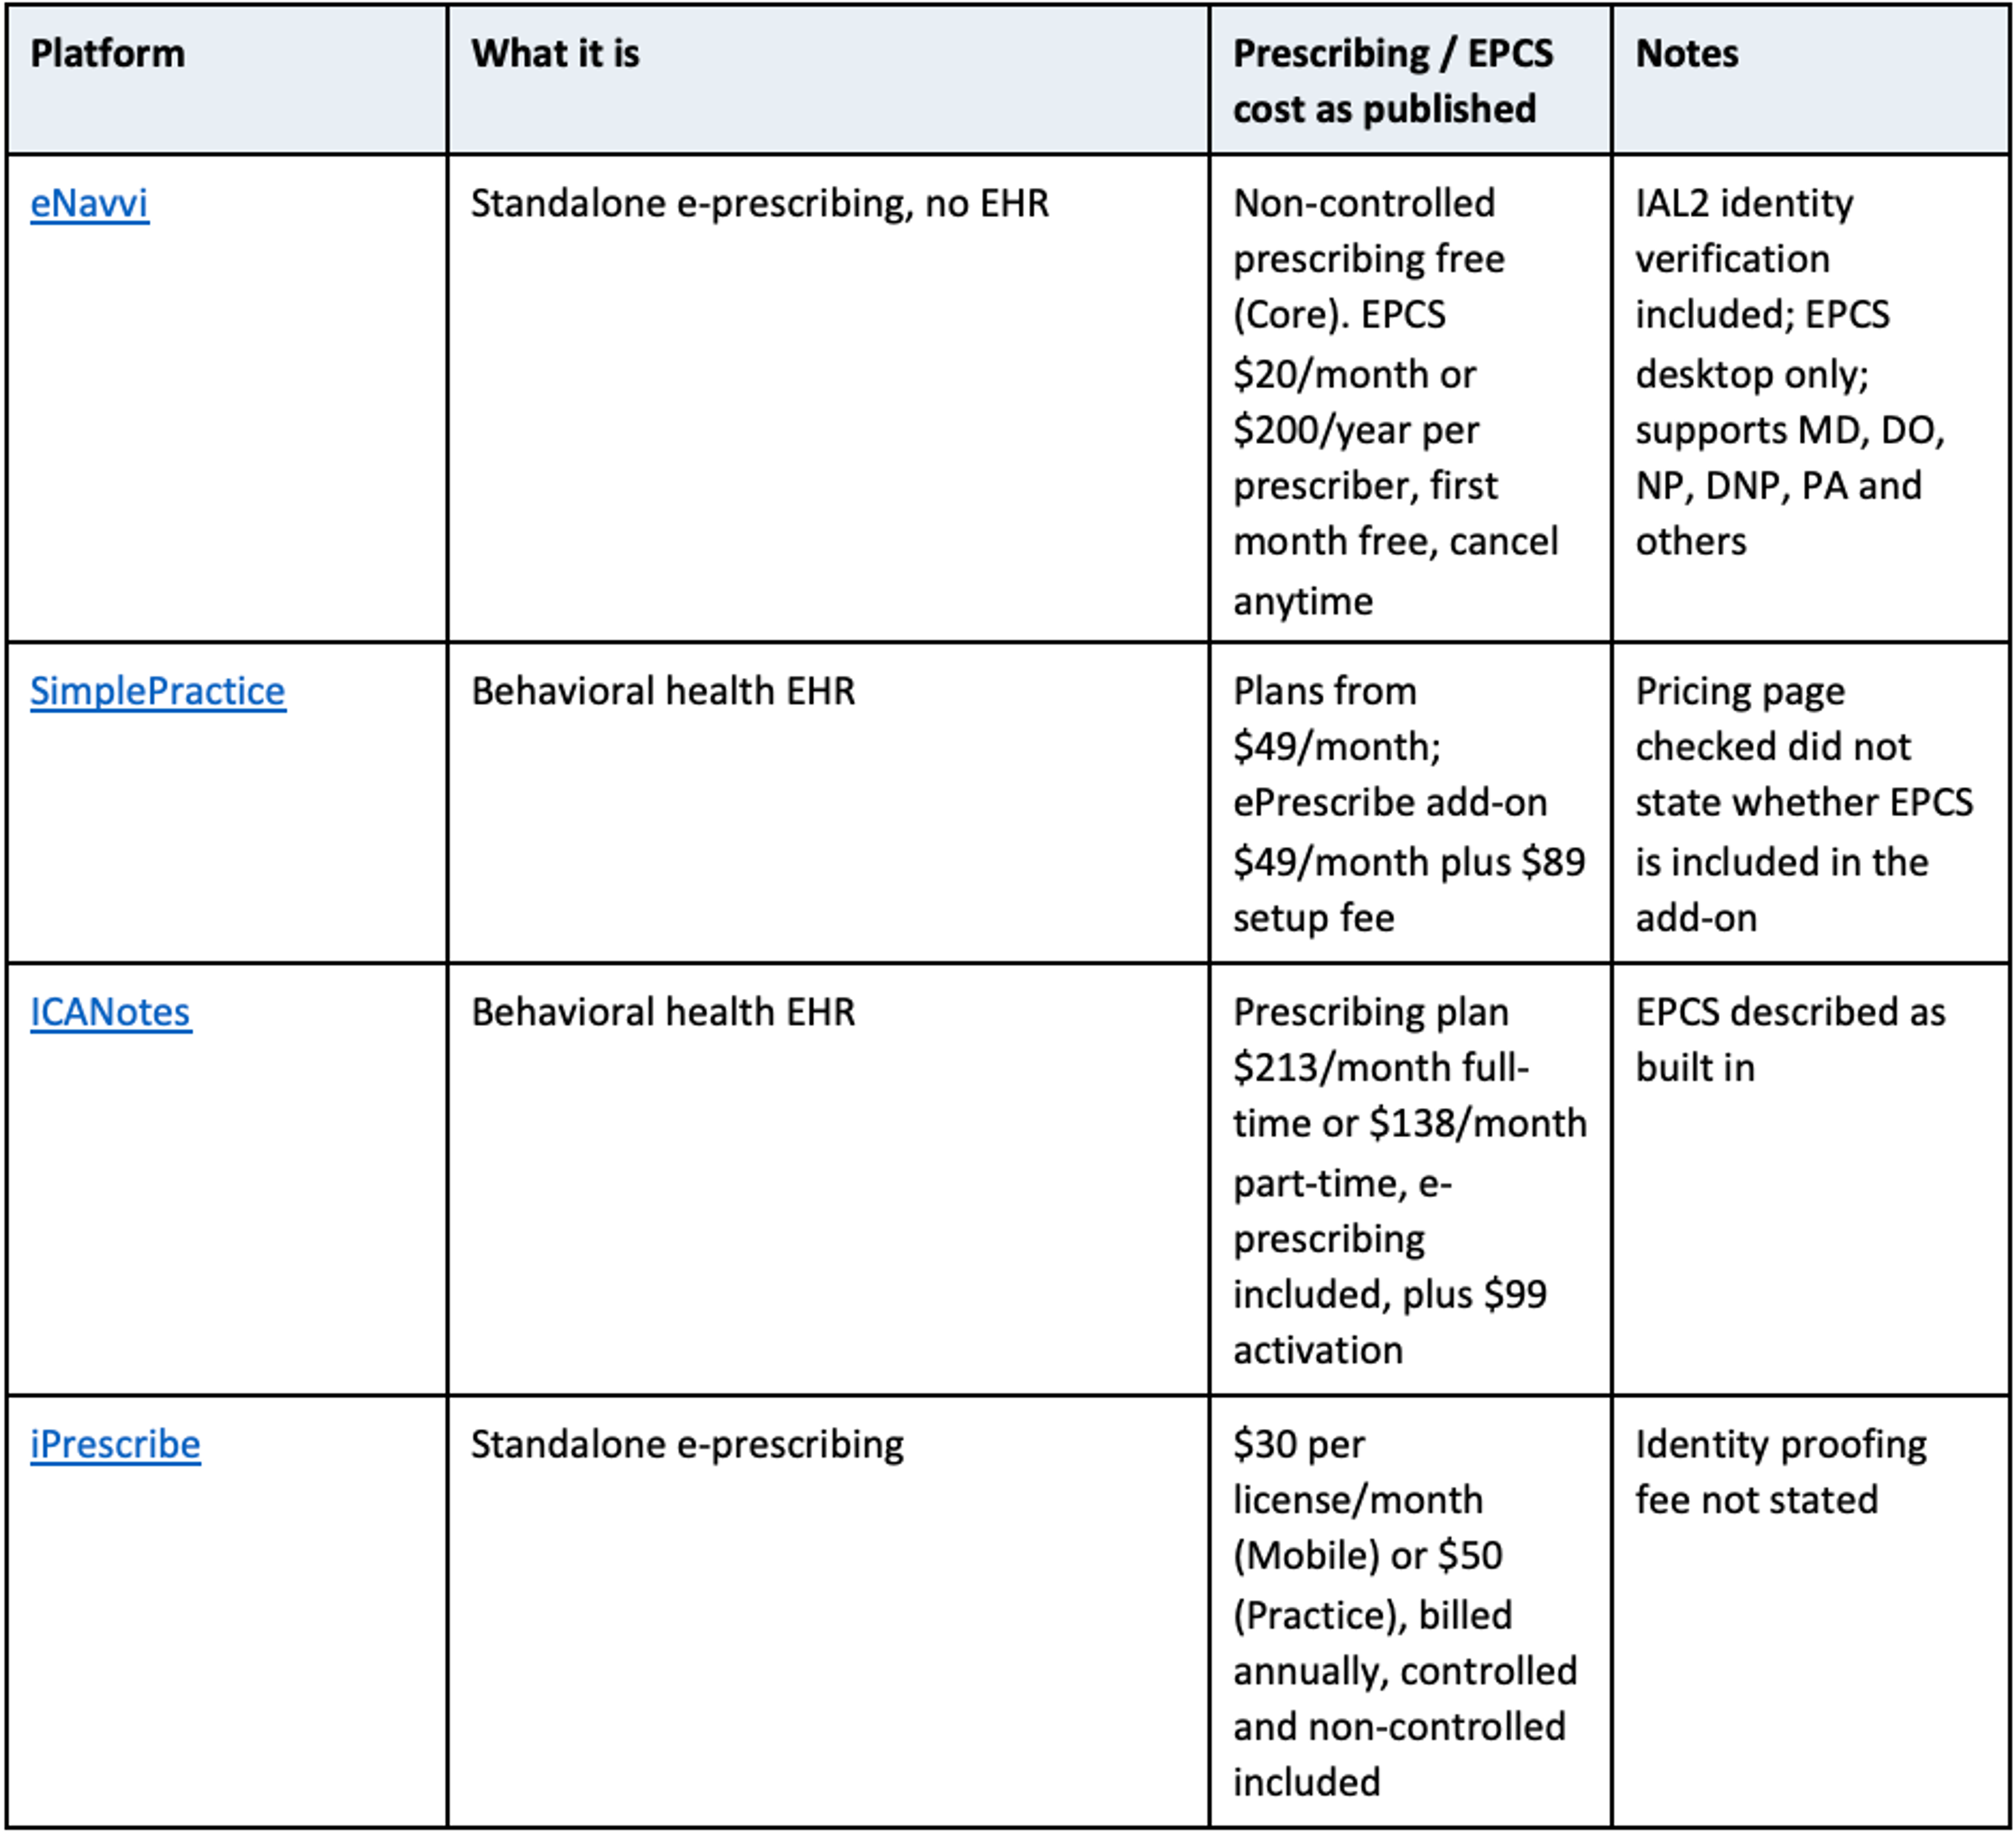
Psychiatry-focused EHRs and standalone tools price EPCS very differently, and the comparison is not like-for-like: an EHR includes charting, scheduling, and billing, while a standalone tool includes prescribing only. The table records what each vendor's public page stated when checked on September 24, 2026. Prices, plan contents, and trial terms change, so confirm with each vendor before deciding. Product names belong to their respective owners.

Two ways to read this. If you already have a system you like for notes and billing and only need prescribing, the standalone options on these published prices cost between $200 and $600 a year per prescriber before any add-ons. If you need an EHR anyway, the prescribing cost is embedded and the decision is about the EHR.

Where eNavvi fits for a psychiatric practice

eNavvi is a standalone e-prescribing platform. Its Core plan is free and covers non-controlled prescribing with real-time pharmacy price comparison, on desktop and mobile. Its EPCS plan costs $20 per month or $200 per year per prescriber after a one-month free trial, is Drummond-certified for Schedules II–V, uses IAL2 identity verification plus Microsoft Authenticator for two-factor signing, and transmits over the Surescripts network (eNavvi pricing). eNavvi supports MD, DO, NP, DNP, and PA prescribers, among others, and states that EPCS is available in every state (eNavvi FAQ). Under 21 CFR 1311.300, you may ask eNavvi, or any EPCS vendor, for its current third-party audit or certification report before you rely on the application.

Three limits worth knowing before you register. EPCS on eNavvi is desktop only, which fits telepsychiatry from a laptop but not signing a stimulant prescription from a phone between sessions. eNavvi is not an EHR: it does not store your progress notes or bill your visits, so you will document the prescription in whatever you use for charting. And like most e-prescribing tools, eNavvi does not replace your state PDMP check, which remains your responsibility at the interval your state requires.

For the general regulatory detail behind EPCS, see EPCS Without the EHR: A Guide for Small Dental and Psychiatric Practices.

Questions psychiatric prescribers ask

Can I prescribe stimulants by telehealth? Federal rules currently allow it under temporary flexibilities extended through December 31, 2026, and state rules vary. Check DEA's current telemedicine guidance and your state board before relying on telehealth prescribing for controlled substances.

Can I e-prescribe three months of a Schedule II stimulant at once? Federal rules allow multiple prescriptions totaling up to a 90-day supply, each dated on the day of issuance, each carrying an earliest-fill date after the first, and each signed individually, if you conclude there is no undue risk of diversion or abuse and your state permits it. Your software must support the earliest-fill-date instruction on each electronic prescription.

Does EPCS satisfy my state's PDMP requirement? No. EPCS is the DEA-compliant way to transmit the prescription. The PDMP check is a separate state obligation with its own timing and documentation rules.

As a PMHNP, does a DEA registration let me prescribe Schedule II? Only if your state grants that authority. DEA registration follows state scope of practice; it does not extend it. Confirm your schedule authority and any collaborative-agreement requirement with your state board before setting up EPCS.

My patient's pharmacy cannot fill the stimulant I sent. Do I have to write a new prescription? Not necessarily. Since 2023, federal rules allow the pharmacy, at the patient's request, to transfer an unfilled electronic controlled-substance prescription once to another pharmacy for initial filling. If you prefer to reissue it yourself, cancel the original first.

Next step

If you already have a way to chart and bill and want prescribing that costs nothing for non-controlled medications and $20 a month for EPCS, eNavvi's pricing page lists the details, and you can register for the free Core plan at enavvi.com. If you are a PMHNP, confirm your controlled-substance authority with your state board first.

Read More
Free E-Prescribing Software: What "Free" Actually Includes and How to Total the Real Cost

If you are a clinician looking for free e-prescribing software, here is the short version. Free tiers usually cover one thing well: sending non-controlled prescriptions electronically. The costs, when they exist, show up in four places: a monthly or annual license, a cap on prescription volume, a paid add-on for controlled substances (EPCS) with its own identity-proofing fee, and setup or contract terms. If you know those four places, you can compare any two tools in about ten minutes.

This guide explains what a free e-prescribing tool should include, where the paid parts hide, and how to total the real cost. It also shows publicly posted pricing from four standalone vendors, including eNavvi, as of September 2026.

What "free e-prescribing" usually means

The phrase covers three different things, and directory sites tend to mix them together.

A free tier inside an EHR. Some electronic health record (EHR) products have offered free or low-cost entry plans that include prescribing. You get prescribing, but you also take on the EHR: its data model, its contract, and its upgrade path. This makes sense if you want the EHR anyway. It is a poor fit if you already have one, or only need to prescribe.

A free trial of a paid product. Many standalone e-prescribing vendors offer 14 to 30 days free. This is a trial, not a free plan. Pricing after the trial is what you are actually evaluating.

A free core product with a paid controlled-substance tier. A smaller group of standalone tools make non-controlled prescribing free indefinitely and charge only for EPCS. eNavvi uses this model: standard e-prescribing is free, and EPCS is a paid subscription. This is the model most likely to match what a search for "free e-prescribing software" is really asking for, so it is worth understanding its boundaries.

The four places cost appears

Whatever the pricing model, the money shows up in one or more of these lines. Ask about all four before you register.

1. License or subscription

Standalone vendors typically price per prescriber per month, often billed annually. Check whether the published number requires an annual commitment and whether it is per prescriber or per practice. A "practice" plan is sometimes cheaper per seat but only if you have enough prescribers to fill it.

2. Volume caps and per-script fees

Some plans include a fixed number of prescriptions per month and move you to a higher tier above it. If your practice writes a high volume of refills or short-course scripts, a cap can matter more than the base price. Ask whether refills, cancellations, and change requests count against the cap.

3. EPCS and identity proofing

Electronic prescribing of controlled substances is almost never free, because the software must meet DEA requirements under 21 CFR Part 1311, including identity proofing of each prescriber and two-factor authentication at signing. Vendors recover that cost in different ways:

  • A monthly EPCS subscription on top of a free or paid core.
  • A separate annual identity-proofing or biometric fee per prescriber.
  • A one-time verification fee at setup.
  • Bundled into a higher per-license price that covers controlled and non-controlled prescribing together.

If you prescribe any Schedule II–V medication, this line is often the largest single cost in the comparison. See our companion piece on what EPCS requires and costs (proposed article; link once published) for the regulatory detail.

4. Setup, onboarding, and contract terms

Look for one-time account setup fees, network verification fees, minimum terms, and cancellation rules. Also ask how long activation takes. A tool that takes ten business days to verify your credentials is a real cost if you need to prescribe this week.

A total-cost worksheet

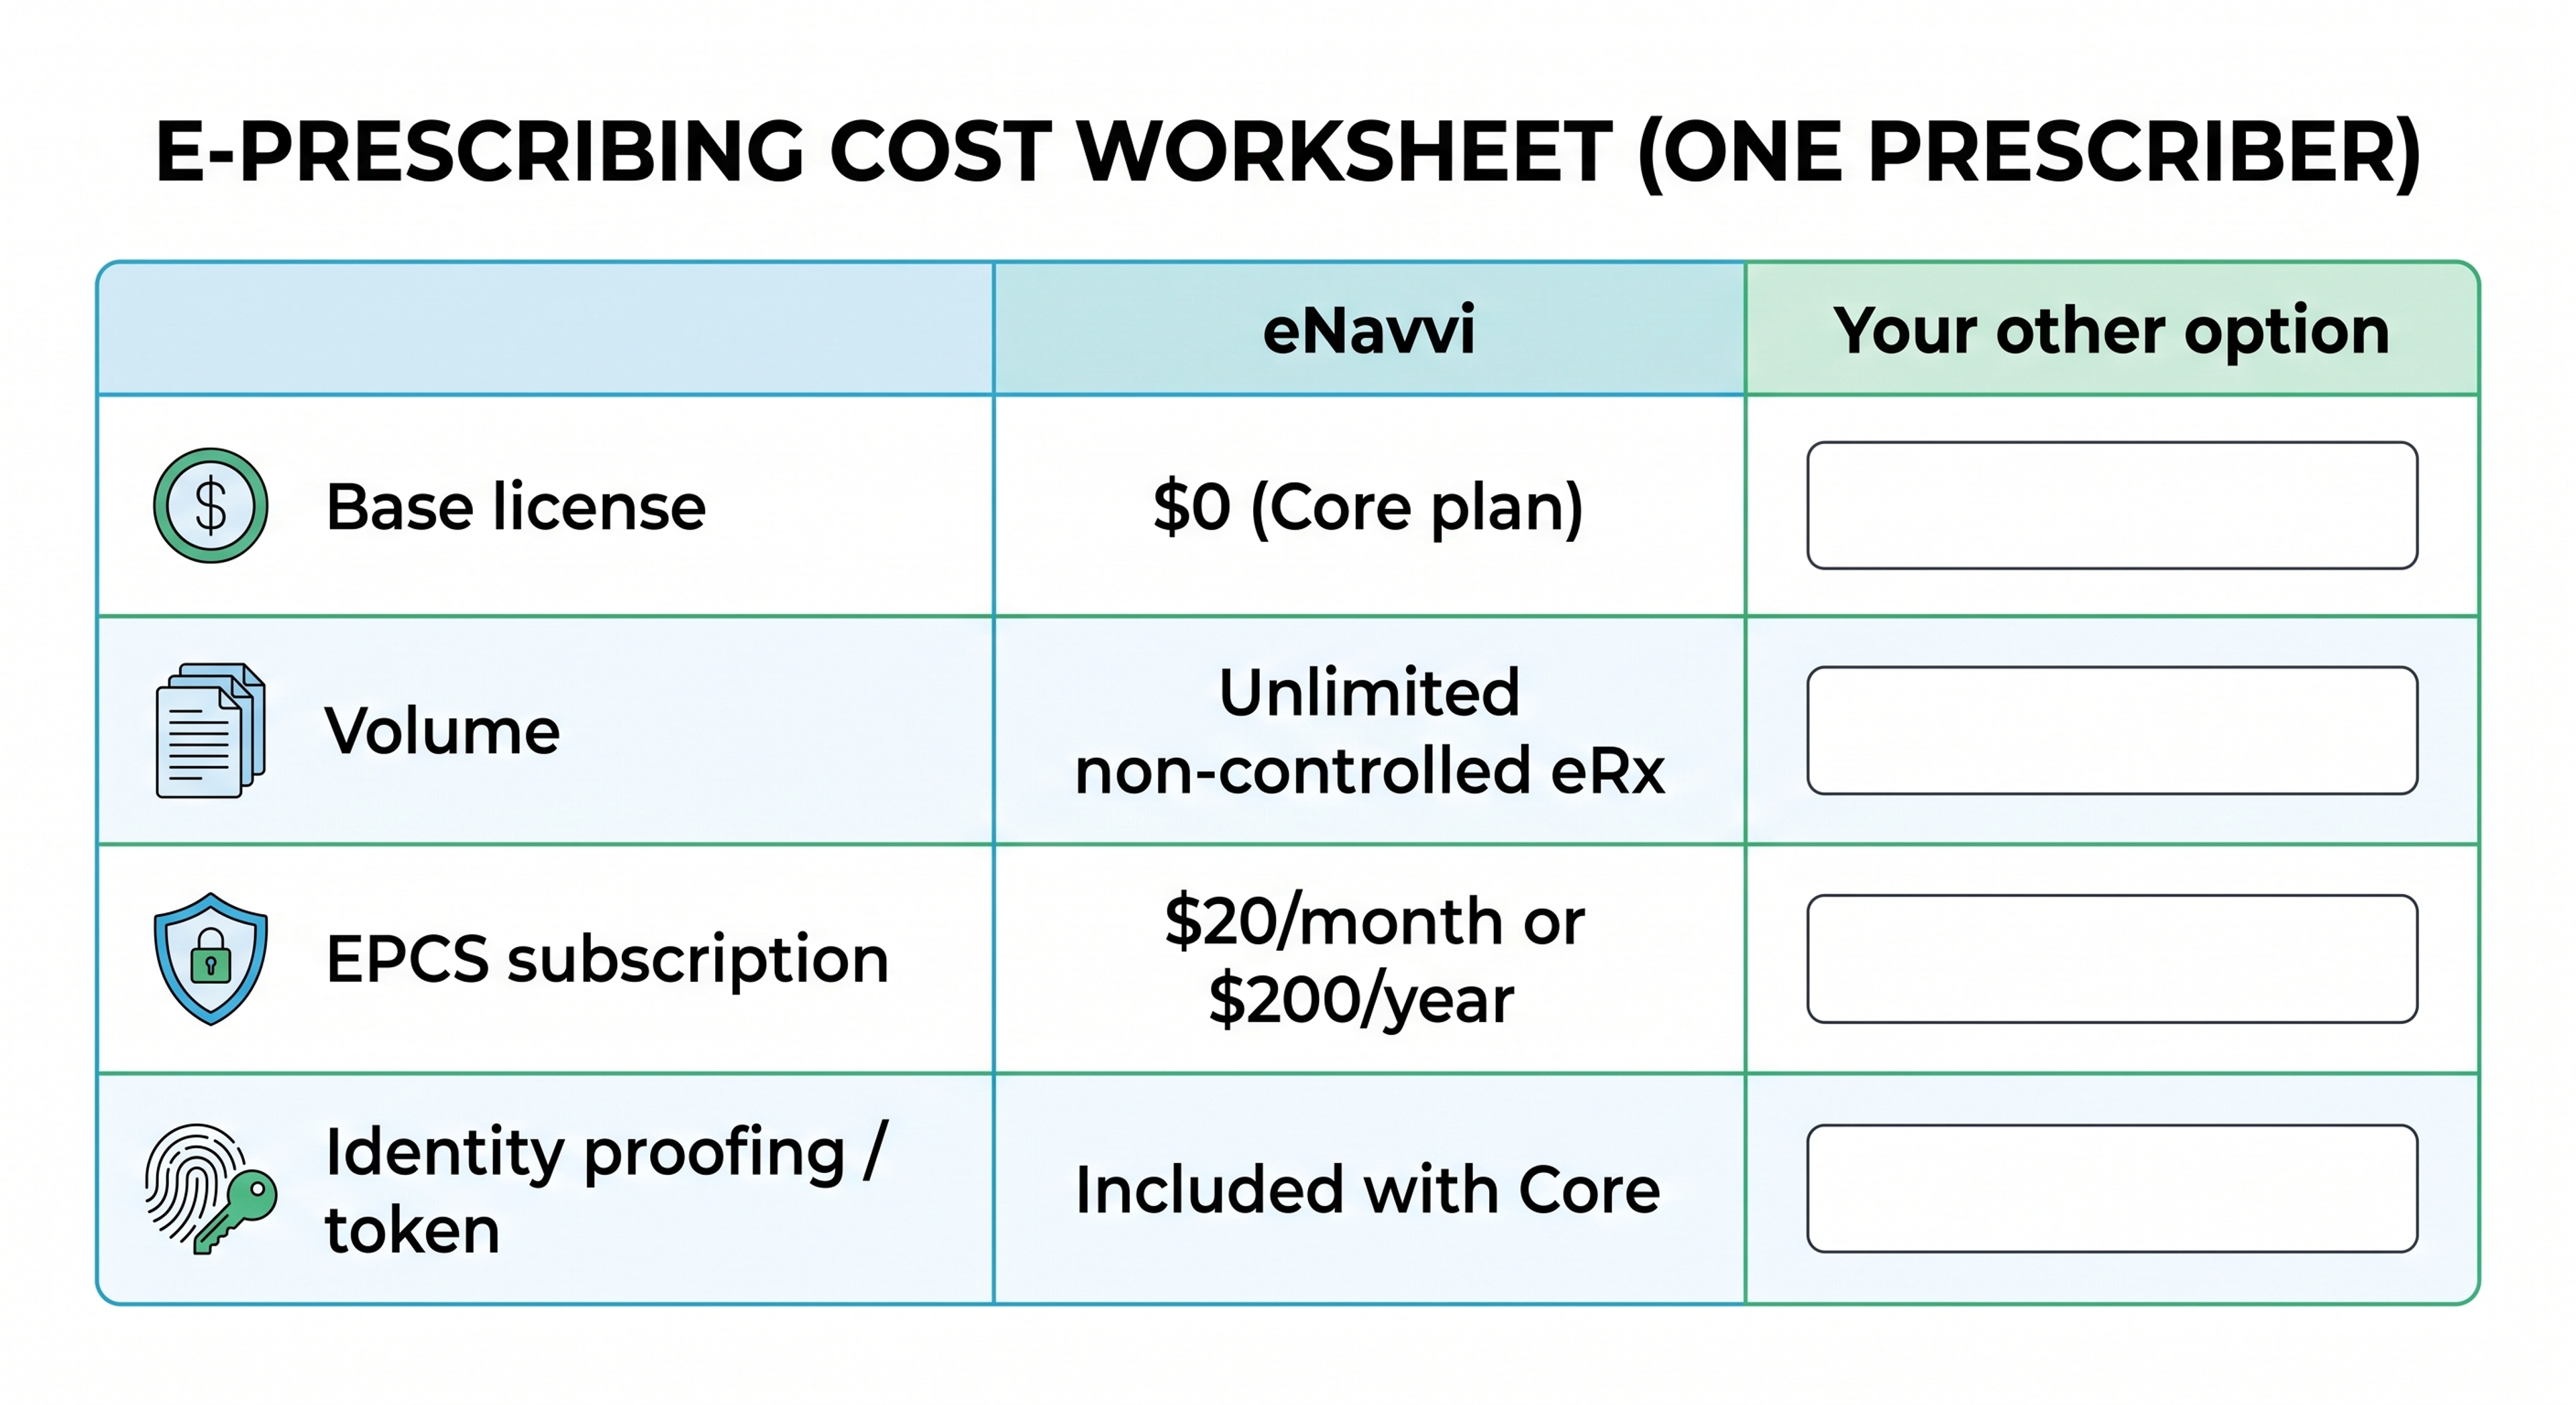
Use the same worksheet for every vendor you evaluate. Put a number or "$0" in each row, and write "unknown" where the vendor does not publish it. Unknowns are a finding in themselves.

Two practical notes. First, calculate the 12-month number for one prescriber, then for your actual headcount. Per-practice plans and annual-only billing change the ranking at different sizes. Second, price is only one column. Certification, network connectivity, and supported prescriber types belong in the same comparison and are covered below.

What free should still include

A free plan is not a good deal if it drops the things that make e-prescribing work. Whatever you pay, confirm these:

Surescripts connectivity or equivalent network access. Electronic transmission to pharmacies runs over the Surescripts network for most of the country. Ask whether the vendor is Surescripts-certified for standard e-prescribing and which transaction types are supported (new prescriptions, cancellations, refill requests, change requests).

A stated fallback when electronic delivery fails. Some vendors fail over to fax when a pharmacy cannot receive an electronic prescription. Others do not. Know which you are getting.

Coverage where you practice. Confirm the tool operates in your state and supports your credential type. Standalone tools vary in whether they accept NPs, PAs, dentists, podiatrists, optometrists, or pharmacists with prescriptive authority.

Security posture you can verify. Ask for the SOC 2 report or equivalent and, for EPCS, the DEA-required third-party audit or certification report. Under 21 CFR 1311.300, EPCS application providers must make that report available to practitioners who use or are considering the application.

Pricing you can read without a sales call. If the base price is not published, budget time to obtain it, and treat the missing number as a cost signal.

What a standalone e-prescribing tool does not do

Standalone prescribing tools are not EHRs. They generally do not chart visits, code and bill encounters, manage schedules, or store the longitudinal record. If you need those functions, you are shopping for an EHR, and the prescribing module comes with it.

A standalone tool also does not replace your judgment about drug interactions, formulary coverage, or prior authorization. Some standalone tools include interaction checking, formulary lookups, or real-time benefit data; others focus on transmission and price transparency. Ask which clinical decision-support features are included rather than assuming.

Where eNavvi fits

eNavvi is a standalone e-prescribing platform that works from a browser or mobile app, independent of any EHR. As of September 2026, its pricing page lists three plans:

  • Core: free. Unlimited non-controlled e-prescribing, real-time pharmacy price comparison, and IAL2 identity verification, on desktop and mobile.
  • EPCS: $20 per month or $200 per year per prescriber, after a one-month free trial, cancel anytime. Adds Drummond-certified electronic prescribing of Schedule II–V controlled substances with two-factor authentication. EPCS requires an active Core account and is currently desktop only.
  • Enterprise: custom pricing for EHR integration, telemedicine enablement, dedicated onboarding, and support commitments.

According to eNavvi's FAQ, the platform operates in all 50 states and Washington, D.C.; currently supports MD, DO, DMD, DDS, DPM, NP, DNP, and PA prescribers; transmits over the Surescripts network with automatic fax failover; and is SOC 2 Type 2 certified. Credential verification typically takes about two hours during business hours.

Put into the worksheet above for a single prescriber who does not prescribe controlled substances, eNavvi's 12-month total is $0. For a prescriber who needs EPCS, it is $200 to $240 depending on billing cycle, with no separate identity-proofing fee listed.

Questions clinicians ask before registering

Is free e-prescribing software safe to use for patient prescriptions? Free pricing does not by itself say anything about safety or compliance. Judge the tool by its network certification, security attestations, and, for controlled substances, its DEA-required audit or certification report. Ask for documents rather than accepting a badge on a homepage.

Can I use a free standalone tool alongside my existing EHR? Usually yes, since standalone tools do not require EHR integration. The tradeoff is that prescriptions written in the standalone tool will not appear in the EHR's medication list automatically unless the vendor offers an integration. Decide whether you will document the prescription in the EHR manually.

Why is EPCS almost never free? DEA rules require identity proofing of each prescriber through an approved provider, two-factor authentication at signing, and periodic third-party audit or certification of the application. Those are recurring costs to the vendor, so they are typically passed through as a subscription, an annual fee, or a bundled higher price.

Does "unlimited prescriptions" ever have a catch? Sometimes the catch is not volume but scope: unlimited non-controlled prescriptions with controlled substances excluded, or unlimited on one platform (mobile) but not another. Read the plan boundaries, not just the word "unlimited."

Next step

If you want to run the worksheet against eNavvi's numbers, the pricing page lists the Core, EPCS, and Enterprise plans, and you can register for the free Core plan at enavvi.com. For questions about prescriber eligibility or state coverage, the FAQ is the fastest source, and the team can be reached through the contact page.

Read More
What EPCS Requires and Costs in 2026: A Prescriber's Checklist

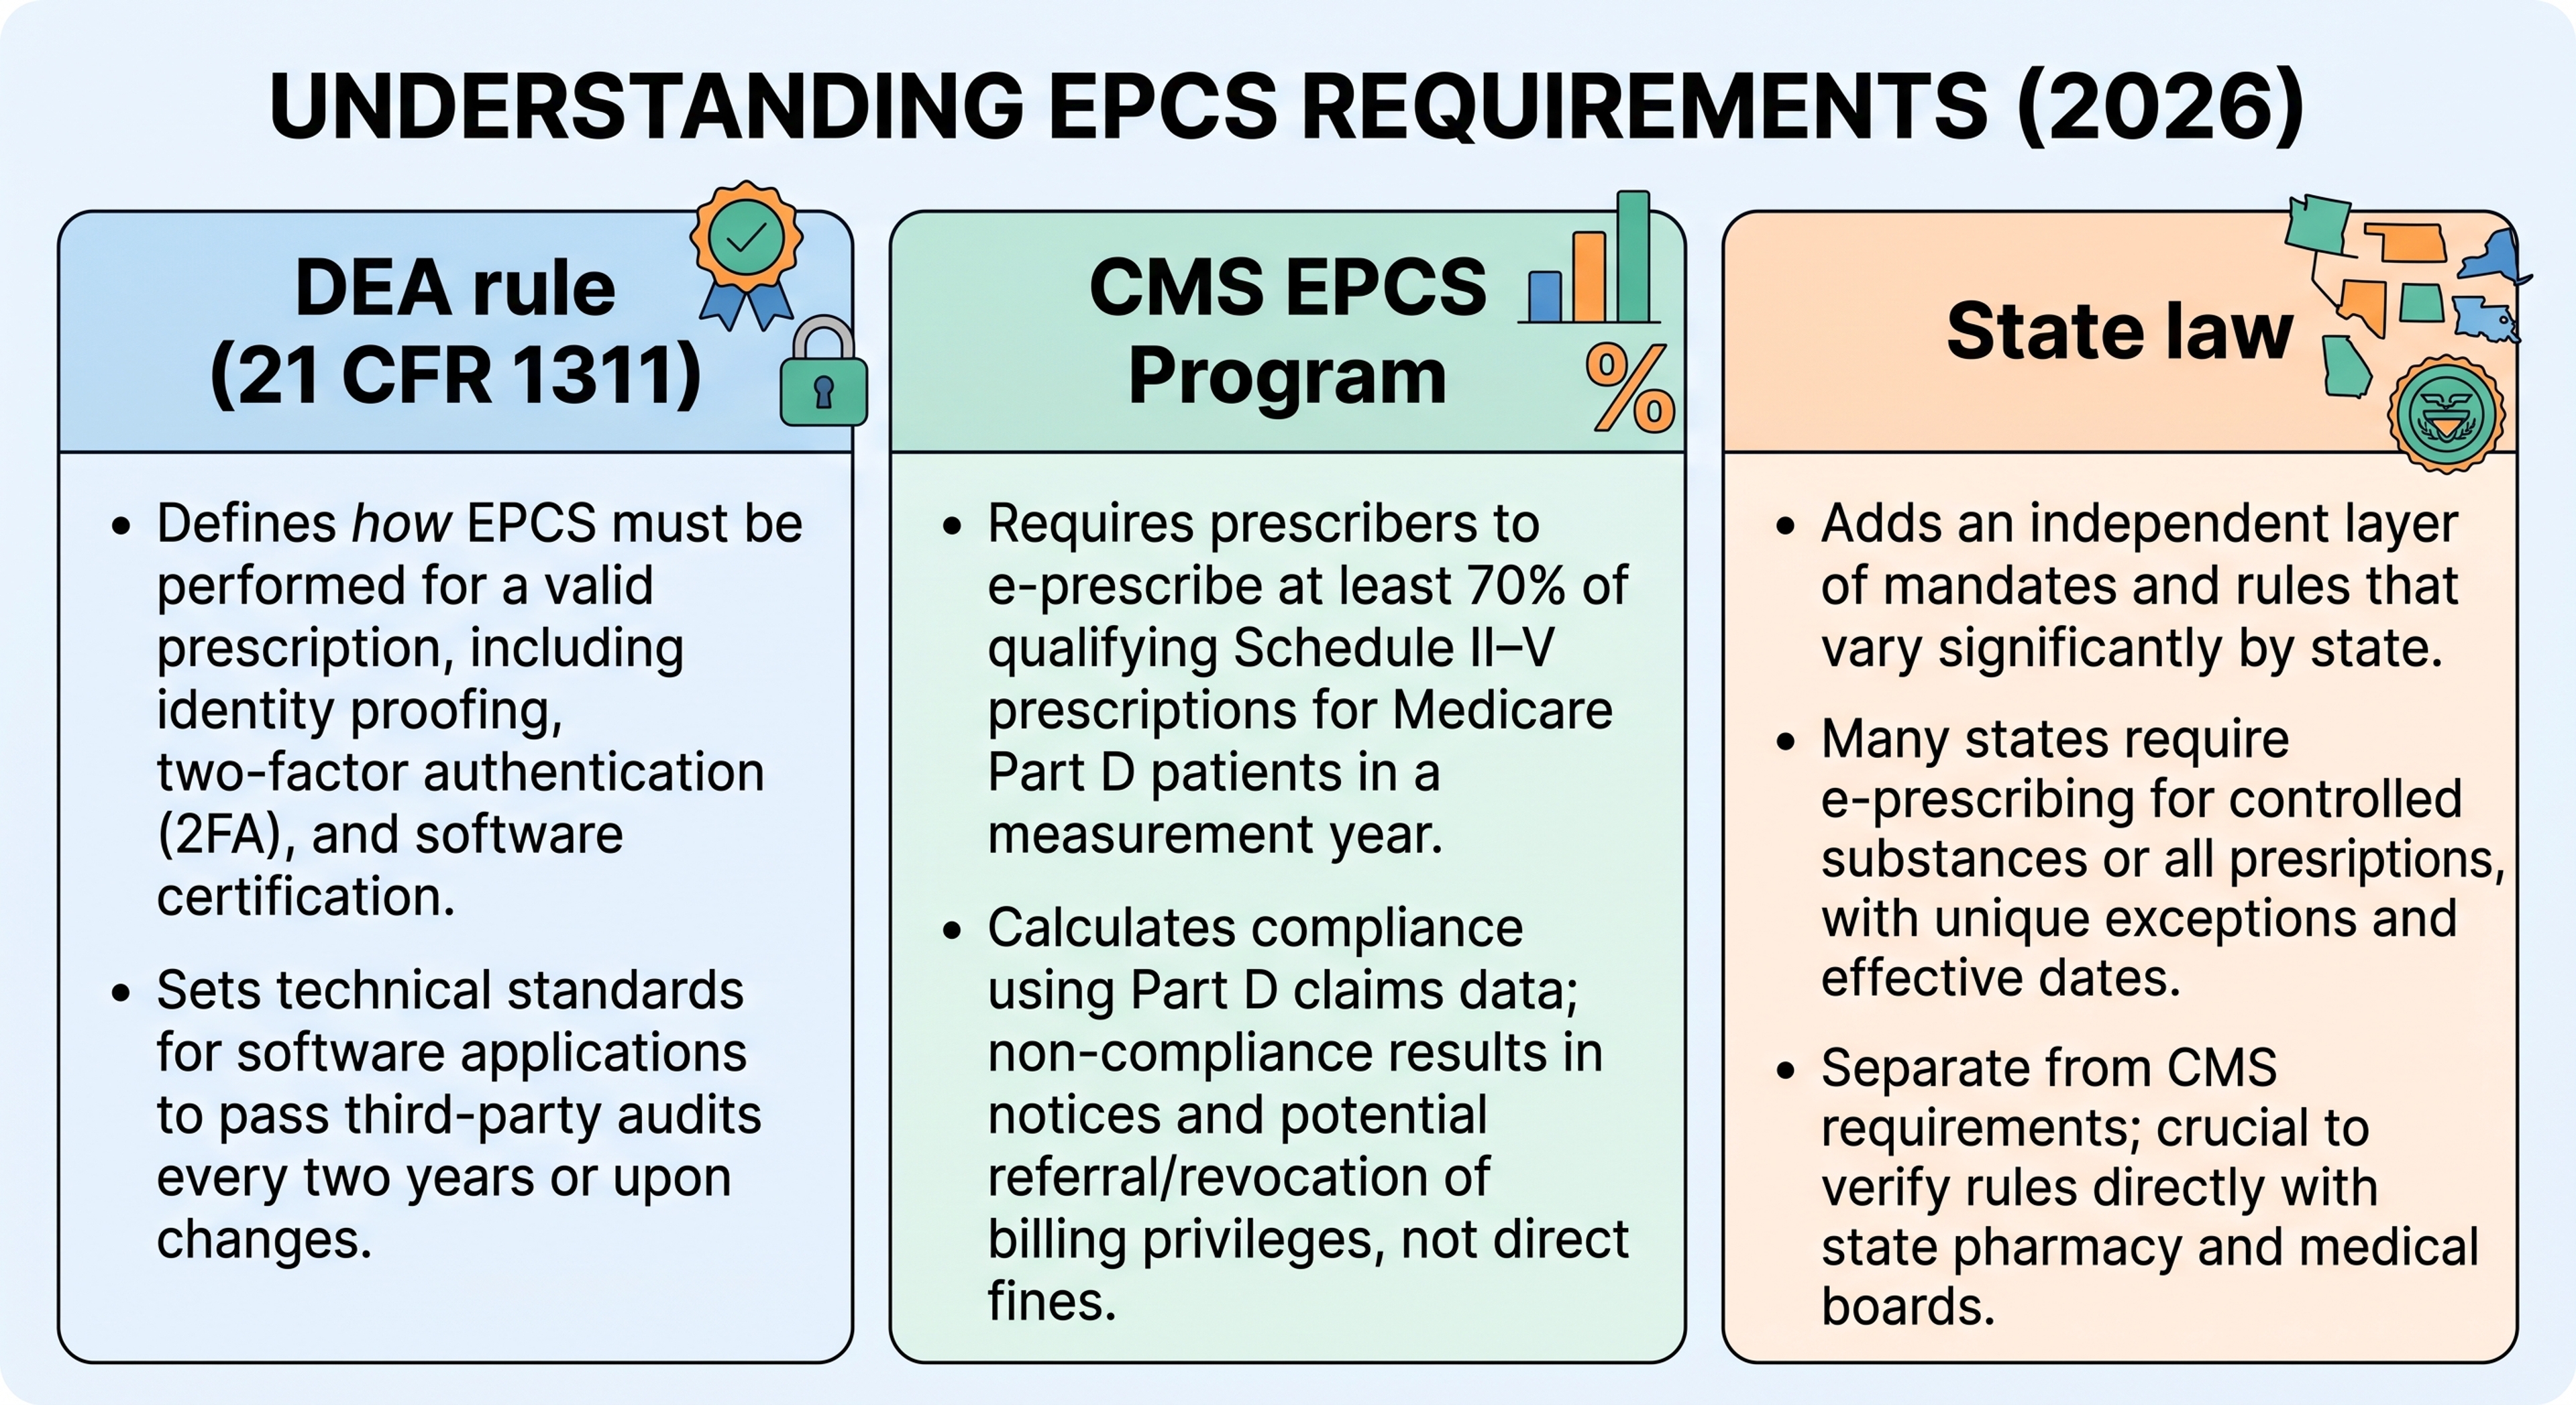
Electronic prescribing of controlled substances (EPCS) is governed by one federal rule and measured by one federal program, and most of the confusion comes from mixing the two. The DEA rule, 21 CFR Part 1311, says what a prescriber and a software application must do for an electronic controlled-substance prescription to be valid. The CMS EPCS Program says how much of your Medicare Part D controlled-substance prescribing must be electronic. State law adds a third layer that varies by state.

This checklist separates the three, explains what each one requires of you as a prescriber, shows what EPCS costs on standalone platforms as of September 2026, and lists the setup steps that most often stall onboarding.

Is EPCS required?

Under DEA rules, no. DEA's regulations permit electronic prescribing of controlled substances but do not mandate it. Practitioners may still issue paper prescriptions with a manual signature, and pharmacies may decline to accept electronic ones (DEA Diversion Control Division, EPCS Q&A).

Under the CMS EPCS Program, effectively yes for most Medicare Part D prescribers. Authorized by Section 2003 of the SUPPORT Act, the program requires prescribers to e-prescribe at least 70% of their qualifying Schedule II–V controlled-substance prescriptions for patients covered under Medicare Part D and Medicare Advantage prescription drug plans in each measurement year (January 1 to December 31). Three exceptions apply:

  • Small prescriber exception, granted automatically to prescribers who issue 100 or fewer qualifying Part D controlled-substance prescriptions in the year.
  • Declared disaster exception, granted automatically in CMS-identified emergency areas.
  • CMS-approved waiver, for prescribers who apply during the fall window and show circumstances beyond their control.

CMS calculates compliance from Part D claims starting in August after the measurement year, and sends non-compliance notices in September. The program does not impose a direct fine. CMS states that non-compliance may be considered in its fraud, waste, and abuse processes, which in some instances could lead to referral or revocation of billing privileges. Prescriptions for beneficiaries in long-term care facilities will not count toward compliance before January 1, 2028 (CMS EPCS Program page, updated June 26, 2026; CMS Getting Started Quick Reference Guide v9.0, January 2026).

Under state law, it depends where you practice. Many states require electronic prescribing for controlled substances or for all prescriptions, with their own exceptions, waivers, and effective dates. CMS notes that its program is separate from state requirements. Check your state board of pharmacy or medical board rather than a vendor roundup, since roundups age quickly.

The practical reading: if you write more than about 100 controlled-substance prescriptions a year for Medicare Part D patients, or practice in a state with a mandate, you need EPCS.

What DEA requires of you, the prescriber

Four things, and none of them is optional.

1. A DEA registration. EPCS does not change who may prescribe controlled substances. You need an active DEA registration and, where your state requires it, a state controlled-substance registration.

2. Identity proofing. Before you can be issued an authentication credential for EPCS, your identity must be verified by an approved credential service provider or certification authority. The rule, 21 CFR 1311.105, requires identity proofing at NIST SP 800-63-1 Assurance Level 3 or higher, which corresponds to Identity Assurance Level 2 (IAL2) under the current NIST 800-63-3 framework. Remote identity proofing is permitted (21 CFR 1311.105; DEA EPCS Q&A). In practice this means submitting a government ID and other verification through the vendor's identity provider, and the credential being issued through two separate channels.

3. Two-factor authentication at signing. To sign a controlled-substance prescription, the application must require two of three factors: something you know (a password or challenge response), something you have (a hard token separate from the computer, meeting at least FIPS 140-2 Security Level 1), or something you are (a biometric meeting DEA's standards). An authenticator app on a phone is a common "something you have." The credential is yours alone; you may not share it, and prescriptions signed with it are your responsibility (21 CFR 1311.115).

4. Affirmative review and signing of each prescription. Staff may prepare a controlled-substance prescription, but the prescriber must review the required information and indicate that it is ready to be signed, then sign it with two-factor authentication. Responsibility for the prescription rests with the prescriber, exactly as with paper (DEA EPCS Q&A).

What DEA requires of the software

You do not have to audit the software yourself, but you should know what to ask for.

Under 21 CFR 1311.300, an electronic prescription application must pass a third-party audit or a DEA-approved certification before it processes controlled-substance prescriptions, and again whenever controlled-substance functionality changes or every two years, whichever comes first. The application provider must make the audit or certification report available to any practitioner who uses or is considering the application (21 CFR 1311.300). Drummond Group is one certification body that tests applications against 21 CFR Part 1311, with recertification on a two-year cycle (Drummond Group).

Two questions to ask any vendor: "Which body certified your EPCS functionality, and when?" and "Can you send me the current certification report?" A vendor that cannot produce the report is telling you something.

Setup checklist

Work through these in order. Most take minutes; the ones that take days are flagged.

Confirm your DEA registration is active and matches the name and address you will use for identity proofing. A mismatch between your DEA record, your government ID, and your NPPES record is the most common reason identity proofing fails.

Check state requirements. Some states require a separate controlled-substance registration, a PDMP account, or state-specific EPCS steps. CMS's own guide reminds prescribers to check state law.

Update your contact information in NPPES and PECOS. CMS uses these records to apply automatic exceptions and to send non-compliance notices. Stale addresses mean missed notices (CMS Quick Reference Guide v9.0).

Choose a certified application and request the certification report. See the questions above.

Complete identity proofing. Have your government ID ready. Timing varies from same-day to more than a week depending on the vendor's identity provider.

Set up two-factor authentication. Install the authenticator app or enroll the biometric or token the vendor uses. Do this on the device you will actually prescribe from.

Configure access controls if you have staff. If staff will prepare prescriptions, set their roles so that only you can sign.

Send a test prescription to a pharmacy that has agreed to receive one, or use the vendor's test pharmacy, and confirm the pharmacy sees it as a controlled-substance prescription.

Optionally, create a HARP account so you can view your CMS EPCS Program compliance status on the CMS EPCS Prescriber Portal each fall and submit a waiver if you ever need one.

Common onboarding problems

The platform is desktop-only for EPCS. Some vendors, including eNavvi, offer EPCS only on desktop while non-controlled prescribing works on mobile. If you prescribe controlled substances from a phone today, plan for that.

Identity proofing fails on a name or address. Use the exact legal name on your ID and make your DEA and NPPES records consistent before you start.

The two-factor device is not where you are. Choose a second factor that travels with you. A hard token left at the office blocks signing at home.

Multi-state prescribers. Confirm the platform supports EPCS in every state where you hold a DEA registration, and that the pharmacy you are sending to accepts EPCS. eNavvi's FAQ states EPCS is available in every state on its platform.

Expecting the software to satisfy CMS for you. The application meets DEA's technical rule. Meeting the CMS 70% threshold is about how you prescribe, not which tool you use. No vendor can enroll you in or exempt you from the CMS program.

Where eNavvi fits

eNavvi is a standalone e-prescribing platform whose non-controlled prescribing is free. Its EPCS plan costs $20 per month or $200 per year per prescriber after a one-month free trial, cancel anytime, and requires an active Core account. According to eNavvi's pricing page and FAQ, the EPCS plan is Drummond-certified for Schedules II–V, uses IAL2 identity verification (included with Core) plus Microsoft Authenticator for two-factor authentication, transmits over the Surescripts network, is available in every state, and is desktop only. Credential verification typically takes about two hours during business hours, and EPCS multi-factor setup adds up to ten minutes. eNavvi requires a DEA registration for EPCS and supports MD, DO, DMD, DDS, DPM, NP, DNP, and PA prescribers.

For a specialty-focused discussion of running EPCS without buying an EHR, see EPCS Without the EHR: A Guide for Small Dental and Psychiatric Practices.

Questions prescribers ask about EPCS

Do I need a hard token? Not necessarily. DEA requires two of three factors. A password plus an authenticator app on a separate device, or a password plus a compliant biometric, satisfies the rule. A hard token is one option, not a requirement.

If I write fewer than 100 controlled-substance prescriptions a year for Part D patients, can I skip EPCS? The CMS small prescriber exception is automatic at 100 or fewer qualifying prescriptions. State law may still require EPCS, and pharmacies increasingly prefer it. Check your state before deciding.

Does EPCS certification expire? Under 21 CFR 1311.300, the application must be re-audited or recertified at least every two years, or sooner when controlled-substance functionality changes. Ask for the date of the vendor's current report.

Can my nurse or assistant send controlled-substance prescriptions for me? Staff may prepare a prescription, but the prescriber must review it, indicate it is ready to sign, and sign it with their own two-factor credential. Sharing the credential is prohibited.

Next step

If you want to see how a standalone EPCS setup compares to your current option, eNavvi's pricing page lists the EPCS plan at $20 per month with the first month free. You can register for the free Core plan at enavvi.com and add EPCS from your account.


Read More
EPCS Without the EHR: What Small Dental and Psychiatric Practices Actually Need

If you run a two-chair dental practice or a solo psychiatry office, you have probably had some version of this conversation with a vendor: yes, you need certified controlled-substance e-prescribing, and yes, one way to get it is to buy a bulky electronic health record system.

That answer has never made much sense. The requirement is real. The bundling is a business model.

What EPCS actually requires

Electronic prescribing of controlled substances comes with three requirements, and none of them is complicated:

You have to prove you are who you say you are. Identity proofing verifies your government-issued ID, your current state authorization to practice, and your DEA registration. You do it once.

You have to authenticate at the moment you sign. Not at login — at signing, each time, using two separate factors. In practice that’s usually a password plus a one-time code on a device you carry.

The software has to be certified. The prescribing application must pass an independent audit confirming it meets the DEA’s requirements, and be re-audited over time.

That’s the whole list. Notice what isn’t on it: an electronic health record. The certification attaches to the prescribing application, not to a records system. Everything beyond those three requirements is packaging.

Federal rules require controlled substances prescribed under Medicare Part D to be transmitted electronically, and most states have added mandates of their own with varying scope and timing. If you write controlled substances at all, you are probably already in scope — and state requirements change often enough that it’s worth checking yours directly rather than relying on what a vendor told you two years ago.

Why dentistry keeps running into this

Dentistry is the clearest case of a specialty that prescribes controlled substances while rarely operating anything resembling an EHR.

Post-operative pain management is a normal part of the work. Dentists have reduced opioid prescribing substantially over the past two decades, and the profession deserves more credit for that than it usually gets — but “less than before” is not “none,” and a single controlled-substance prescription after a surgical extraction puts the practice inside the requirement.

Meanwhile the software in a typical dental office is practice-management software: scheduling, charting, claims, imaging. Some of those systems offer EPCS as a paid add-on. Many don’t, and the ones that do often price it for a multi-location group rather than a two-operatory practice. The independent dentist ends up choosing between a module they can’t justify and a workflow that’s running out of road.

Why psychiatry runs into it harder

Psychiatry has the same structural problem with worse arithmetic.

A psychiatrist managing a panel of patients on maintenance medication is prescribing controlled substances continuously — not occasionally, not as an edge case, but as a routine part of nearly every follow-up. Controlled-substance prescribing isn’t a corner of the practice. For many psychiatric practices it is the practice.

Small psychiatric practices, telepsychiatry practices, and PMHNP-owned clinics are also among the least likely to have bought a full EHR. The care model doesn’t demand one. The prescribing rules do demand certified EPCS. That gap is where a lot of clinicians are currently improvising.

What a standalone setup looks like

eNavvi was built by physicians for exactly this shape of problem: prescribing that works on its own, without an EHR underneath it.

You search medications, compare real-time cash prices at pharmacies near your patient, and send the prescription electronically anywhere in the country. Non-controlled prescribing is free, permanently. EPCS — the identity proofing, the two-factor signing, the certified application — is $20 per month after a one-month free trial, and you can cancel at any time.

Twenty dollars is roughly the point at which the build-versus-buy question stops being interesting. It’s less than most EPCS add-on modules, and considerably less than an EHR bought to obtain a single feature.

The platform is HIPAA compliant, SOC 2, and LegitScript approved, and it’s used by more than 4,000 prescribers.

The part your patients notice

There’s a second reason small practices end up here, and it has nothing to do with the DEA.

When a patient doesn’t fill a prescription, you usually don’t find out. Cost is a frequent reason, and it disproportionately affects the patients least likely to raise it with you. Dental patients are often uninsured or paying out of pocket for procedures their plan excludes. Psychiatric patients frequently face high deductibles and formulary restrictions on precisely the medications that work.

Seeing the cash price at the pharmacy down the street — before the patient leaves — turns that from a conversation you never have into one that takes fifteen seconds.

Where to start

If you prescribe controlled substances and don’t have certified EPCS, confirm what your state requires, then get identity proofing done. It has the longest lead time and it’s the step people put off.

You can create an eNavvi account and prescribe non-controlled medications free, then decide about EPCS once you’ve seen whether the workflow fits your practice.

Read More
How Independent and Grocery-Chain Pharmacies Are Competing on Cash Price

Two contradictory trends are true of American pharmacy at the same time in 2026: the market for filling prescriptions has never been more consolidated, and cash-price prescribing has never had more legitimate competition driving it down. For prescribers deciding where to route a script — particularly for cash-pay or high-deductible patients — understanding both trends at once is more useful than treating either one in isolation.

The Consolidation Side of the Story

Prescription dispensing revenue in the U.S. is heavily concentrated. The top 15 pharmacy companies accounted for nearly three-quarters of total U.S. dispensing revenue in 2025, and the four largest — CVS Health, Walgreens, Cigna, and UnitedHealth Group — together accounted for more than half of it on their own [1]. That concentration has been building for over a decade: from 2010 to 2025, CVS Pharmacy and Walgreens alone announced the acquisition of more than 6,000 locations from smaller competitors [1].

Pharmacy benefit managers (PBMs) sit at the center of that concentration. The three largest PBMs — CVS Caremark, Express Scripts, and OptumRx — administer pharmacy networks that individually span tens of thousands of locations, and plan sponsors routinely shift entire member populations between them; CalPERS, for example, moved certain Medicare HMO and PPO plans from OptumRx to CVS Caremark effective January 1, 2026 under a new multi-year contract [2]. Each such transition resets which pharmacies sit inside a given patient's preferred network, independent of anything the prescriber or patient did — a structural volatility that independent pharmacies have less scale to absorb than national chains with contracts across every major PBM.

The Countertrend: Independent Pharmacies Are Still Growing

Despite that pressure, independent pharmacy counts have not collapsed — they've grown. Between 2015 and 2025, the number of independent retail pharmacies in the U.S. increased by 321 stores, a 1.4% gain, while retail chain pharmacy counts fell by 5,742 stores, a 14.1% decline over the same period [3]. That trend continued into 2026, with 67 more independent pharmacies operating nationally compared with the year before [3]. The trade association representing PBMs points to this data as evidence that reimbursement rates for independents have held up [3] — a claim worth taking with the appropriate grain of salt given the source, but the underlying store-count data is independently verifiable and tells a real story: independents are not simply being priced out of existence, even as their share of PBM-driven volume shrinks.

The mechanism behind that survival, for many independents, has shifted from insurance-network participation toward cash-price competitiveness — discount programs, direct partnerships with cash-pay platforms, and membership or subscription pricing that doesn't depend on being in a PBM's preferred network at all.

GLP-1 Pricing as the Clearest Case Study

Nowhere is the cash-price competition more visible right now than in GLP-1 weight-management drugs. In 2026, Novo Nordisk cut the cash price of Wegovy and Ozempic by 30%, from $499 to $349 per month for patients paying without insurance, extending that pricing to roughly 70,000 retail pharmacies nationwide, including Walmart and Costco [4]. Eli Lilly has taken a parallel approach with Zepbound, offering vials priced between $349 and $499 per month depending on dose through its LillyDirect program, with retail pickup available at Walmart [4].

The pattern is consistent across both manufacturers: direct-to-consumer and cash-pay pricing programs are now routinely undercutting standard insured copays for patients on high-deductible plans or without GLP-1 coverage at all, and that pricing is increasingly available through ordinary retail pharmacy pickup rather than mail-order-only programs. For prescribers, this means the "what does this actually cost without insurance" conversation has a materially different answer in 2026 than it did even a year or two earlier, and it's worth checking current cash pricing rather than relying on a remembered figure.

It's also worth noting the gap between manufacturer direct-to-consumer pricing and standard retail cash pricing at the same pharmacy chain can be substantial — as of mid-2026, a standard cash-pay box of Wegovy at a typical retail pharmacy still runs well above $1,300, compared with the $349 manufacturer-direct price for the same drug through NovoCare Pharmacy [4]. That gap means the specific channel a patient uses, not just the pharmacy chain, determines what they actually pay — a distinction worth confirming rather than assuming based on the pharmacy's name alone.

Why Independents Often Punch Above Their Weight on Service

Price is only part of what keeps independent pharmacies competitive. Independents are disproportionately more likely to offer same-day compounding, direct pharmacist consultation without an appointment, and flexibility on delivery or curbside pickup that larger chains standardize less consistently across locations. For patients on complex regimens — polypharmacy in older adults, pediatric dosing that requires compounding, or specialty conditions where a pharmacist relationship matters for adherence — those service differences can matter as much as a few dollars of price difference. None of that shows up in a PBM network directory, which is part of why prescribers who default to "in-network" as the only routing criterion may be missing options that serve a given patient better on both price and service.

What Grocery-Chain Pharmacies Bring to the Table

Grocery-chain pharmacies (Kroger, Safeway, Vons, and similar regional chains) occupy a middle position between large national chains and independents: broad geographic reach similar to a national chain, but often more willing to participate in cash-pay partnership programs the way independents do, since pharmacy is typically a traffic-driver for the grocery business rather than the sole profit center. That combination — retail-chain reach with independent-style cash-pay flexibility — is part of why cash-price partnership networks increasingly include grocery pharmacies alongside independents rather than treating them as a separate category.

What This Means for Where You Route a Script

  • For cash-pay or high-deductible patients, the lowest-cost pharmacy is no longer reliably the same one it was even a year ago. Manufacturer cash-price programs and pharmacy-specific discount partnerships change faster than most prescribers can track manually.
  • Independent and grocery-chain pharmacies are a legitimate cash-price option, not a fallback. The data on independent pharmacy growth suggests these locations are competing successfully on price and service, not simply surviving on inertia.
  • A platform that shows real-time cash pricing across multiple pharmacy types — independent, grocery-chain, and national retail — gives a more complete picture than checking one chain's app or assuming a single "usual" pharmacy is still the cheapest option for a given patient.
  • When a PBM contract transition happens (as with the CalPERS example above), a patient's previously preferred pharmacy can change without either the prescriber or patient initiating anything — worth a quick verification at the next visit for patients on maintenance medications, rather than assuming last year's pharmacy routing still applies.

Where eNavvi Fits

eNavvi's pharmacy network spans independent and grocery-chain pharmacies alongside cash-pay partners including Mark Cuban Cost Plus Drug Company and Amazon Pharmacy, letting clinicians compare real-time cash pricing across pharmacy types at the point of prescribing rather than defaulting to whichever pharmacy a patient has used before. See real-time cash pricing across pharmacy types on eNavvi.

Read More
Perimenopause Prescribing in 2026: Why Compounding Is the Missing Piece

Estrogen-based hormone replacement therapy prescribing has more than doubled since 2018. The most dramatic increase is in the perimenopause population: as of February 2026, 1 in 20 women aged 45–54 has an active estrogen-based HRT prescription, a 184% increase across the study period. Patch use has tripled. Vaginal cream use has quadrupled. The FDA’s removal of boxed warnings on HRT products last year accelerated a trend that was already well underway.

For prescribers, the clinical demand is clear. The operational challenge is that the FDA-approved HRT formulary doesn’t cover every patient—and the patients it doesn’t cover are arriving in numbers that compounding pharmacies were not built to handle through phone calls and fax machines.

Why the Perimenopause Wave Is Different

Earlier symptom recognition. The cultural shift toward recognizing and treating perimenopause—driven by patient advocacy, social media, and high-profile coverage—means women are presenting earlier, often in their late 30s and early 40s, with irregular cycles, vasomotor symptoms, sleep disruption, and mood changes. These patients often have fluctuating hormone levels rather than the flat postmenopausal profile, which makes fixed-dose commercial products a less precise fit.

Post-boxed-warning confidence. The FDA’s removal of the black box warning on HRT products—pointing to newer delivery methods and evolving safety evidence—has materially increased both prescriber willingness and patient demand. Clinicians who were reluctant to initiate HRT during the post-WHI era are now prescribing with more confidence, and patients are actively requesting it.

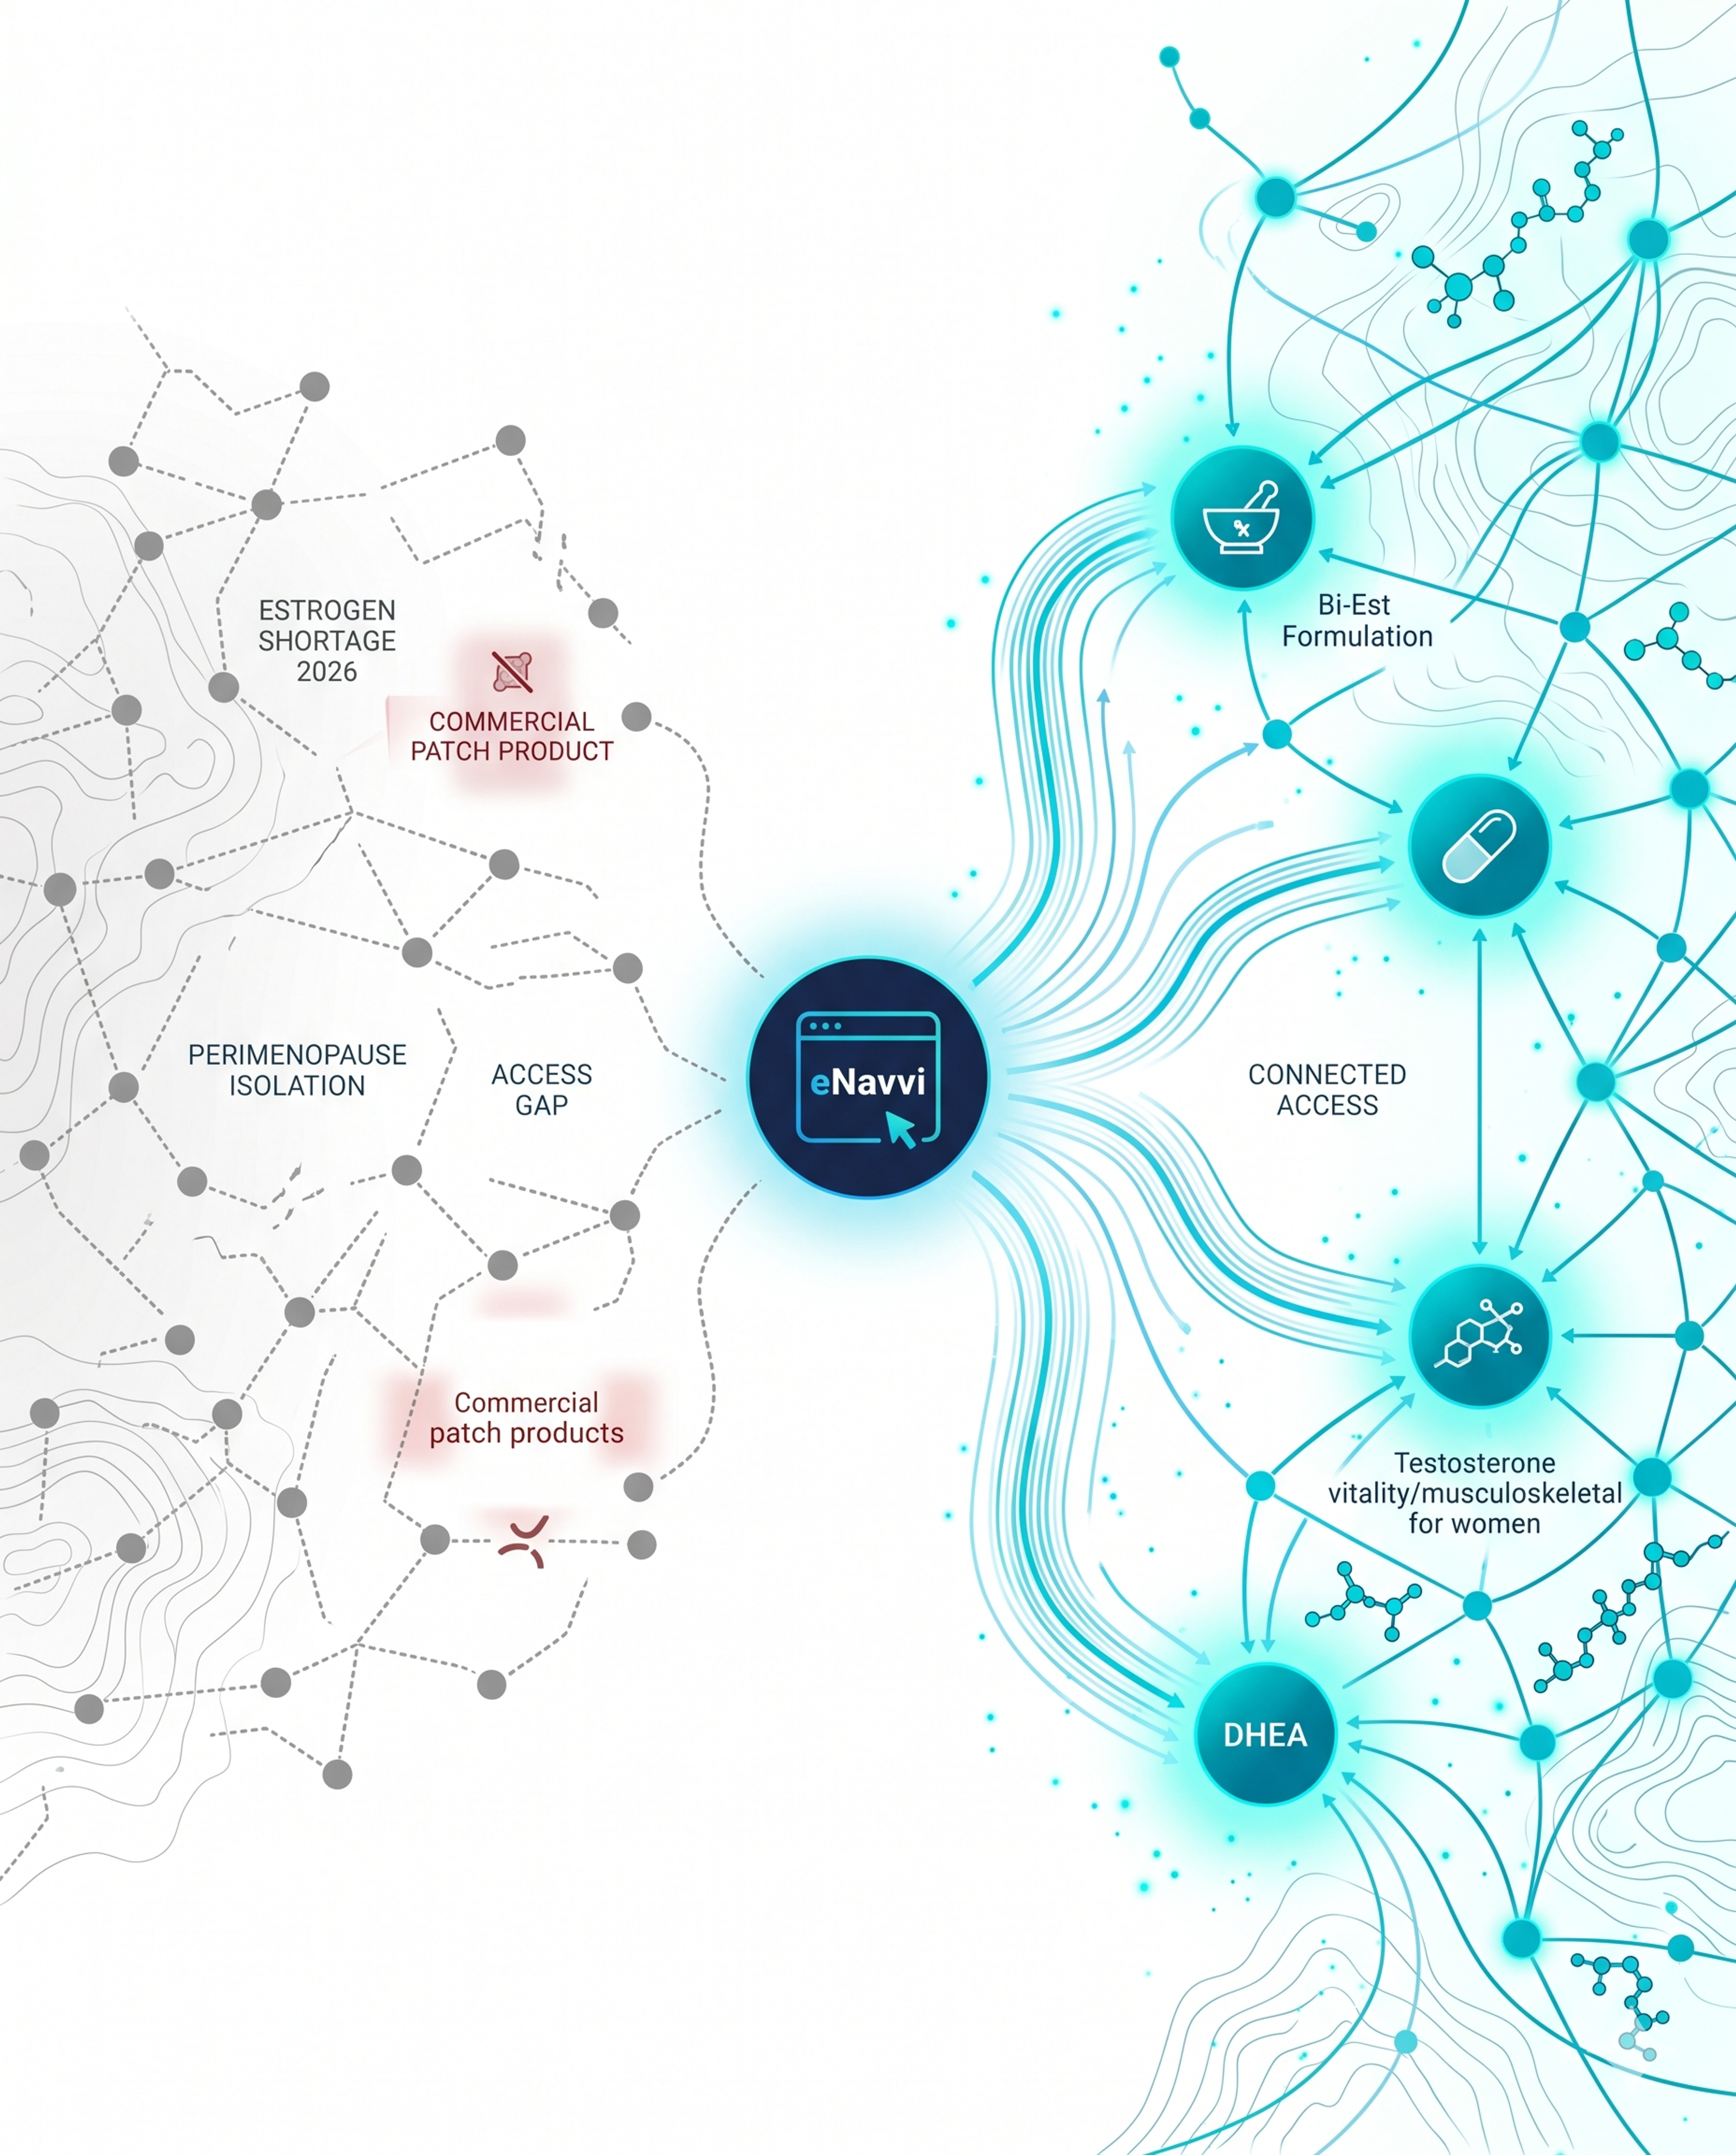
Supply chain fragility. The 2026 estrogen patch shortage exposed how concentrated the commercial HRT supply chain has become. When Bayer discontinued Climara and only three manufacturers remained for the majority of U.S. estradiol patches, any demand spike creates nationwide access problems. Prescribers who rely exclusively on commercial products are one shortage away from having no options for their patients.

The Compounding Formulary for Perimenopause

Compounded estradiol and Bi-Est. Bi-Est (a combination of estriol and estradiol, typically in an 80:20 ratio) remains the most commonly prescribed compounded estrogen preparation. It is available in transdermal creams, vaginal preparations, and sublingual troches. Compounding allows precise dose titration—starting at low doses for early perimenopause and increasing as the patient’s symptoms and labs dictate—without being locked into the fixed-dose increments of commercial products.

Micronized progesterone. The most commonly prescribed compounded progesterone form. Prometrium (the FDA-approved oral micronized progesterone) comes in 100 mg and 200 mg capsules. Compounding pharmacies prepare micronized progesterone in capsules, topical creams, vaginal inserts, and sublingual troches at custom doses—typically 25 mg to 400 mg—allowing prescribers to match the dose to the clinical scenario rather than the pharmacy shelf.

Testosterone for women. There is no FDA-approved testosterone product for women in the United States, despite strong evidence supporting low-dose testosterone for hypoactive sexual desire, energy, and musculoskeletal health in perimenopausal and postmenopausal women. Compounded testosterone creams (typically 0.5–2 mg daily) are the primary prescribing pathway. This is a compounding-only category.

DHEA. Compounded DHEA—both oral and vaginal—fills a gap for genitourinary symptoms and broader adrenal support. Intrarosa (prasterone) is the only FDA-approved vaginal DHEA product, but compounding offers dose flexibility and combination formulations that the single commercial product cannot.

Why the Prescribing Workflow Is the Bottleneck

The clinical knowledge exists. The formulations exist. The bottleneck is the workflow between prescriber and pharmacy.

When 5% of a practice’s prescriptions are compounded, that’s manageable. When 30–50% are compounded—as is common in menopause-focused practices—it’s a scaling crisis. eNavvi eliminates the parallel workflow. Prescribers access the full HRT compounding formulary—Bi-Est, progesterone, testosterone, DHEA—alongside FDA-approved medications from a single digital platform, with electronic prescriptions sent to PCAB-accredited pharmacies and transparent cash pricing visible before the script is sent.

The Perimenopause Prescribing Workflow That Scales

Browse eNavvi’s compounded HRT templates—Bi-Est, micronized progesterone, testosterone, DHEA—across PCAB-accredited pharmacies with transparent cash pricing. Free for prescribers. Electronic prescribing. No faxes.

Get Started Free at eNavvi.com →

Frequently Asked Questions

Q: Why has HRT prescribing increased so dramatically?

A: Estrogen-based HRT prescribing has more than doubled since 2018, driven by increased perimenopause recognition, cultural destigmatization, updated clinical guidelines, and the FDA’s removal of boxed warnings on HRT products. As of February 2026, 1 in 20 women aged 45–54 has an active estrogen-based HRT prescription.

Q: Is there an FDA-approved testosterone product for women?

A: No. Despite clinical evidence supporting low-dose testosterone for hypoactive sexual desire and other symptoms in perimenopausal and postmenopausal women, there is no FDA-approved testosterone product for women in the United States. Compounded testosterone creams from PCAB-accredited pharmacies are the primary prescribing pathway.

Q: What is Bi-Est and how is it prescribed?

A: Bi-Est is a compounded combination of estriol and estradiol, typically in an 80:20 ratio. It is available in transdermal creams, vaginal preparations, and sublingual troches. Bi-Est allows prescribers to provide a bioidentical estrogen preparation with dose flexibility not available in commercial fixed-dose products. It is prescribed through compounding pharmacies—platforms like eNavvi allow electronic prescribing to PCAB-accredited pharmacies with transparent pricing.

Read More
Compounded Finasteride, Minoxidil, and Beyond: A Prescriber’s Guide to Hair Loss Compounding

The hair loss treatment market is projected to reach $7.28 billion by 2032, and compounding pharmacies are an increasingly important part of that landscape. For prescribers, the shift is already obvious in the exam room: patients are arriving with questions about topical finasteride, compounded minoxidil formulations, and multi-agent combinations they found through telehealth platforms or social media. They want to know if these treatments actually work—and they want their physician, not an algorithm, to prescribe them.

The clinical case for compounded hair loss treatments is straightforward. FDA-approved products cover a narrow range of dosage forms and concentrations. Many patients need something different—a topical alternative to oral finasteride because of side-effect concerns, a higher-concentration minoxidil for treatment-resistant cases, or a multi-ingredient formulation that addresses several pathways at once. Compounding fills that gap. But prescribers need to understand what’s available, what’s supported by evidence, and what the FDA has flagged as a safety concern.

Why Commercial Hair Loss Products Don’t Fit Every Patient

The FDA-approved toolkit for androgenetic alopecia has been the same for years: oral finasteride (1 mg daily), oral dutasteride (0.5 mg, off-label in the U.S.), and topical minoxidil in 2% or 5% solutions or foam. These work—combined oral finasteride and minoxidil has shown a mean increase of roughly 30 hairs per square centimeter at 24 weeks in clinical studies—but they leave significant gaps.

Oral finasteride side effects. A meaningful percentage of male patients decline or discontinue oral finasteride due to sexual side effects (decreased libido, erectile dysfunction) or neuropsychiatric concerns (depression, anxiety, cognitive fog). These patients need a topical alternative—but there is no FDA-approved topical finasteride product on the market. The only pathway is compounding.

Concentration limitations. Over-the-counter minoxidil maxes out at 5%. Some patients—particularly those with treatment-resistant vertex thinning or diffuse thinning—respond better to higher concentrations (6%, 8%, or even 10% in some compounded formulations). Compounding pharmacies can also formulate minoxidil without propylene glycol for patients who develop contact dermatitis from the commercial vehicle.

Multi-pathway therapy. Alopecia is multifactorial: androgen-driven miniaturization, inflammation, microbial overgrowth, and vascular insufficiency can all contribute. A single-agent product addresses one mechanism. Compounded multi-agent topicals—combining a DHT blocker, a vasodilator, an anti-inflammatory, and an antifungal in one application—can address several pathways simultaneously, improving adherence by reducing the number of products a patient has to apply.

The Compounded Hair Loss Formulary: What Prescribers Should Know

Topical finasteride. The most-prescribed compounded hair loss ingredient. Typical concentrations range from 0.025% to 0.1% in solution or gel vehicles. The clinical rationale is straightforward: deliver the 5-alpha reductase inhibitor directly to the scalp to reduce local DHT while minimizing systemic absorption and its associated side effects. Patient satisfaction data from telehealth platforms has been positive, and a growing body of retrospective evidence supports efficacy. However, prescribers must be aware that the FDA issued a safety alert in April 2025 specifically addressing compounded topical finasteride. The agency noted 32 adverse event reports between 2019 and 2024—including erectile dysfunction, depression, and suicidal ideation—and emphasized that topical application does not eliminate systemic absorption. Patients must be counseled on these risks, and prescribers should document informed consent.

Topical minoxidil (compounded concentrations). Beyond the commercial 2% and 5% options, compounding pharmacies prepare minoxidil in concentrations from 6% to 15%, in vehicles ranging from solutions and foams to hydrating gels. Higher concentrations are typically reserved for patients who have plateaued on 5% or who have extensive thinning. Compounders can also formulate minoxidil without alcohol or propylene glycol—a meaningful advantage for patients with sensitive scalps or contact dermatitis.

Topical dutasteride. Dutasteride inhibits both type 1 and type 2 5-alpha reductase enzymes, making it a more potent DHT blocker than finasteride (which targets only type 2). Oral dutasteride is not FDA-approved for hair loss in the United States, though it is approved for this indication in South Korea and Japan. Topical dutasteride is available only through compounding, typically at concentrations of 0.01% to 0.1%. Long-term comparative data from Korea suggest dutasteride may outperform finasteride in sustained hair regrowth, and the topical route offers the same systemic-avoidance rationale as topical finasteride.

Latanoprost. A prostaglandin analog originally approved for glaucoma, latanoprost has shown the ability to increase hair density and prolong the anagen (growth) phase of the hair cycle. It is sometimes included in compounded multi-agent topicals. Clinical data is limited but promising—particularly for eyebrow restoration and frontal hairline thinning where traditional DHT blockers are less effective. Long-term scalp safety data is not yet available, so prescribers should use latanoprost as a targeted addition rather than a standalone therapy.

Ketoconazole. The antifungal agent ketoconazole has a dual role in hair loss compounding: it reduces Malassezia overgrowth on the scalp (a contributor to follicular inflammation and seborrheic dermatitis) and has demonstrated weak anti-androgenic properties. Most evidence supports its use as an adjunct ingredient in multi-agent formulations rather than a primary treatment. Compounded concentrations typically range from 1% to 2%, often combined with finasteride and minoxidil.

Spironolactone (topical). Topical spironolactone is an important compounded option for female pattern hair loss, where oral finasteride and dutasteride are contraindicated. At concentrations of 2% to 5%, topical spironolactone acts as a local anti-androgen without the systemic side effects (hyperkalemia, menstrual irregularity) associated with the oral form. Compounded formulations combining spironolactone, minoxidil, and tretinoin are increasingly common for female patients.

The FDA Safety Landscape: What Prescribers Cannot Ignore

Compounded hair loss formulations occupy a regulatory space that requires prescriber vigilance. None of these topical formulations are FDA-approved, which means the agency has not evaluated their safety, efficacy, or quality prior to marketing. That does not make them illegitimate—compounding under section 503A of the Federal Food, Drug, and Cosmetic Act is a well-established practice for patient-specific needs—but it does place an outsized responsibility on the prescriber and the pharmacy.

The April 2025 FDA safety alert on compounded topical finasteride is the most important recent development. The agency specifically noted that some patients were told by prescribers or telehealth platforms that topical application carried no risk of systemic side effects. That claim is inaccurate. Finasteride absorbs through the skin into the bloodstream, and topical use can produce the same adverse events reported with oral finasteride. The alert also raised concern about inadvertent transfer to household members—particularly women of childbearing potential, given finasteride’s teratogenic risk.

For prescribers, the takeaway is not to avoid compounded topical finasteride—it is to prescribe it responsibly. That means informed consent that mirrors the oral finasteride risk profile, explicit instructions on application technique and transfer prevention, documentation that the patient understands the off-label nature of the formulation, and selection of a PCAB-accredited compounding pharmacy that validates potency and ingredient quality. The quality of the pharmacy matters as much as the quality of the prescription.

Why Pharmacy Selection Is the Prescriber’s Most Underrated Decision

Hair loss compounding has exploded in the telehealth era. Direct-to-consumer platforms like Hims, Keeps, and Ro have introduced millions of patients to compounded finasteride and minoxidil—but the clinical oversight on those platforms varies enormously, and the compounding pharmacies behind them are not always transparent about their accreditation or testing protocols.

For physician-directed prescribing, pharmacy selection should be based on accreditation, not convenience. PCAB (Pharmacy Compounding Accreditation Board) accreditation means the pharmacy has been independently validated for potency testing, ingredient sourcing, beyond-use dating, and compounding consistency. When a prescriber sends a topical finasteride 0.05%/minoxidil 8% order to a PCAB-accredited pharmacy, there is a validated process behind the preparation. When the same order goes to an unaccredited pharmacy, there may not be.

This is where eNavvi changes the workflow. Rather than researching individual compounding pharmacies, calling to confirm formulation capabilities, and faxing prescriptions manually, prescribers can use eNavvi’s digital platform to browse pre-formulated hair loss templates across a network of PCAB-accredited compounding pharmacies—with transparent cash pricing visible before the prescription is sent. The patient gets a compounded product from a quality-validated source. The prescriber gets a workflow that doesn’t require a fax machine or a phone call. And both get pricing transparency that the telehealth platforms rarely offer.

Building a Hair Loss Compounding Workflow That Scales

Know the evidence—and its limits. Compounded hair loss formulations are supported by a growing body of retrospective data, case series, and real-world evidence. But they are not backed by the randomized controlled trials that FDA-approved products have undergone. Prescribers should present compounded formulations as clinically reasonable options within a shared decision-making framework, not as guaranteed solutions.

Document informed consent for topical finasteride. Given the FDA’s April 2025 alert, informed consent for compounded topical finasteride should cover systemic absorption risk, known side effects (sexual, neuropsychiatric), transfer risk to household members (especially women of childbearing age), and the non-FDA-approved status of the formulation. This is a clinical and medicolegal imperative.

Route prescriptions to accredited pharmacies. PCAB accreditation is the clearest signal of compounding quality available. For hair loss formulations—where potency variation directly affects outcomes and safety—sending prescriptions to an accredited pharmacy is not optional, it’s standard of care.

Digitize the workflow. Compounded hair loss prescribing should not mean a return to fax machines. eNavvi gives prescribers electronic access to a PCAB-accredited compounding network with hair loss formulation templates, transparent cash pricing, and a prescribing workflow that matches the efficiency of any EHR—without the limitation of being locked out of compounding pharmacies.

Frequently Asked Questions

Q: Is compounded topical finasteride safe?

A: Compounded topical finasteride uses the same active ingredient as FDA-approved oral finasteride but is not itself FDA-approved. The FDA issued a safety alert in April 2025 noting 32 adverse event reports (2019–2024) including erectile dysfunction, depression, and suicidal ideation. Topical application does not eliminate systemic absorption. Prescribers should counsel patients on these risks, document informed consent, and prescribe only from PCAB-accredited compounding pharmacies that validate potency and ingredient quality.

Q: What is the advantage of compounded hair loss formulations over commercial products?

A: Compounded formulations offer customizable concentrations (e.g., minoxidil above 5%), alternative delivery vehicles for patients with sensitivities, ingredients not available commercially as topicals (finasteride, dutasteride, spironolactone), and multi-agent combinations that address multiple hair loss mechanisms in a single application. This flexibility allows prescribers to tailor treatment to individual patient profiles rather than fitting every patient into the same two or three commercial products.

Q: How do I prescribe compounded hair loss treatments through eNavvi?

A: eNavvi provides a free digital prescription platform that connects directly to a network of PCAB-accredited compounding pharmacies. Prescribers can browse pre-formulated hair loss templates (topical finasteride, high-concentration minoxidil, dutasteride, multi-agent combinations), compare transparent cash pricing across pharmacies, and send compounded prescriptions electronically. No faxing, no phone calls, and no separate workflow for compounded versus FDA-approved medications.

Read More
Women’s HRT in 2026: The Estrogen Shortage, the Access Gap, and Where Compounding Fits

Hormone replacement therapy prescriptions for women aged 50–65 have increased 86% since 2021. The FDA removed boxed warnings on HRT products last year, citing evolving evidence on safety and newer delivery methods. Menopause awareness has gone mainstream, driven by high-profile advocacy, media coverage, and a generation of women demanding better care. By every measure, 2026 should be the best year in decades for women’s access to hormone therapy.

Instead, prescribers are fielding calls from patients who can’t fill their estradiol patch prescriptions.

The estrogen transdermal patch shortage—driven by a convergence of surging demand, limited manufacturers, tariff pressures on overseas production, and the ripple effects of Bayer’s 2023 discontinuation of its Climara patch—has created a real-time access crisis for women on stable HRT regimens. Major pharmacy chains are reporting delays. Patients are scrambling between pharmacies. Prescribers are rewriting prescriptions for alternative formulations mid-cycle.

This moment is forcing a broader conversation about women’s HRT access—one that every prescriber should be part of. Here’s what’s happening, what your options are, and where compounding pharmacy fits into the picture.

What’s Driving the Estrogen Patch Shortage

The shortage isn’t a single-cause problem. It’s the predictable result of demand growth colliding with supply fragility.

Demand surge. The FDA’s removal of boxed warnings on HRT products was a watershed moment. For two decades after the 2002 Women’s Health Initiative, prescribers were cautious about HRT—and many avoided prescribing it altogether. The warning removal, combined with updated clinical guidelines and growing patient demand, triggered a prescribing surge that the supply chain was not built to absorb. HRT prescriptions for women are up 86% since 2021, according to Epic Research data, and the growth shows no sign of slowing.

Manufacturer consolidation. After Bayer discontinued its Climara estradiol patch in late 2023, the U.S. transdermal estrogen market consolidated around just three primary manufacturers: Sandoz, Viatris (formerly Mylan), and Amneal. When demand spikes against a concentrated supply base, shortages propagate faster and resolve more slowly. There simply aren’t enough production lines to flex capacity quickly.

Tariff and supply chain pressure. Tariffs on overseas pharmaceutical manufacturing have added cost and complexity to the transdermal patch supply chain, with several estradiol patch components sourced internationally. These pressures compound (no pun intended) the demand-supply imbalance and make the shortage timeline less predictable.

The clinical preference for transdermal delivery. Transdermal estradiol carries a lower risk of blood clots compared to oral formulations because it bypasses first-pass hepatic metabolism. This safety advantage has made patches the preferred delivery method for many prescribers—which means the shortage is hitting the formulation that clinicians most want to prescribe.

The Menopause Care Gap: A Shortage on Top of a Shortage

The estrogen patch shortage is making headlines, but it’s layered on top of a deeper structural problem: the menopause care gap itself.

The prescriber shortage is real. Data from over 5,400 women treated between 2016 and 2023 shows that only 17% of women seeking menopause-related care received prescription treatment for their symptoms—with dramatic variability across provider specialties. Many primary care physicians, internists, and family medicine providers received minimal menopause training during residency. The result is that millions of symptomatic women either don’t receive treatment, receive suboptimal treatment, or face long wait times to see a menopause-trained specialist.

Access is unevenly distributed. Women in rural areas, women without specialist access, and women whose prescribers are not comfortable initiating HRT face disproportionate barriers. When you add a supply shortage on top of a prescriber shortage, the access gap widens further—and the patients who were already underserved bear the greatest burden.

The conversation is changing. The positive trend in all of this is awareness. Menopause advocacy organizations, celebrity voices, and legislative action (including state-level menopause workplace accommodation bills) have pushed women’s midlife health into the mainstream. More women are asking for HRT. More prescribers are willing to prescribe it. The infrastructure to deliver it—supply chain, trained providers, accessible pharmacy options—is what needs to catch up.

Where Compounded HRT Fits—and Where It Doesn’t

Compounded hormone therapy is not a blanket replacement for FDA-approved products. That distinction matters, and prescribers should be clear-eyed about it.

FDA-approved HRT products should remain the first-line option when they are available and meet the patient’s clinical needs. Dozens of FDA-approved estrogen, progesterone, and combination products exist in various strengths and delivery systems. These products have undergone rigorous review for safety, efficacy, and manufacturing consistency. Both ACOG and the Endocrine Society recommend FDA-approved formulations as the starting point for menopausal hormone therapy.

Compounded HRT becomes clinically relevant in specific circumstances:

When FDA-approved products are unavailable. The current estrogen patch shortage is a concrete example. When a patient on a stable transdermal estradiol regimen cannot fill her prescription because patches are on backorder, the prescriber faces a clinical decision: switch to an oral formulation (with a different risk profile), switch to a different delivery system the patient hasn’t used before, or consider a compounded transdermal estradiol preparation that delivers the same active ingredient through the same route. The last option maintains therapeutic continuity when the commercial product is temporarily inaccessible.

When the patient needs a non-standard strength or dosage form. FDA-approved products come in fixed doses. Some women require titration to a strength between available options—particularly during the initiation phase or when fine-tuning a regimen for symptom control with minimal side effects. Others need a dosage form that isn’t commercially available: a specific cream concentration, a sublingual troche, or a combination preparation that simplifies a multi-product regimen.

When the patient has allergies or sensitivities to inactive ingredients. Patch adhesives, preservatives, dyes, and fillers in commercial products can cause contact dermatitis or other reactions. Compounding allows the active hormone to be delivered in a vehicle free of the specific allergen—a meaningful clinical consideration for women who react to patch adhesives, which is not uncommon.

When combination therapy is appropriate. Some prescribers prefer to combine estrogen and progesterone—or estrogen with testosterone or DHEA—in a single preparation. While the evidence base for specific multi-hormone compounded combinations is more limited than for individual FDA-approved products, combination compounding is widely used in clinical practice to simplify patient regimens and improve adherence.

The Quality Caveat: Why Pharmacy Selection Is the Clinical Decision

Critics of compounded HRT raise a legitimate concern: quality variability. The National Academies documented potency deviations in compounded hormone preparations as high as 26% from labeled amounts. For hormone therapy—where precise dosing directly affects symptom control, endometrial safety, and cardiovascular risk profile—that variability matters.

But the answer to quality variability is not to deny patients access to compounded hormones when they have a legitimate clinical need. The answer is to send those prescriptions to pharmacies that can document their quality.

PCAB-accredited compounding pharmacies represent approximately 8% of U.S. pharmacies. They undergo on-site inspections, demonstrate compliance with USP ⟨795⟩ and ⟨797⟩ compounding standards, verify ingredient sourcing from FDA-registered suppliers, maintain documented potency testing protocols, and ensure staff competency through ongoing assessment programs. For prescribers who compound HRT, the quality conversation is really a pharmacy selection conversation—and accreditation is the clearest available quality signal.

eNavvi’s network requires PCAB or equivalent accreditation from every pharmacy partner. The strategic alliance with ACHC (announced February 2026) provides member pharmacies with a direct accreditation pathway, including a $1,000 discount on PCAB fees. When a prescriber writes a compounded HRT order through eNavvi, the pharmacy on the other end has met a quality threshold that 92% of U.S. pharmacies have not.

What Prescribers Should Do Right Now

Communicate proactively with patients on estrogen patches. If your patients are on transdermal estradiol, don’t wait for them to call you when the pharmacy can’t fill. Reach out now with a plan: confirm their current prescription status, discuss alternative formulations (gels, creams, oral options), and establish a compounding pharmacy relationship as a backup if their preferred product remains unavailable.

Know the full HRT formulation landscape. The estrogen delivery options go well beyond patches and pills. Transdermal gels and creams (both FDA-approved and compounded), vaginal preparations for genitourinary symptoms, sublingual troches, and injectable estradiol are all available. Compounding pharmacies expand this further with Bi-Est formulations (estriol and estradiol combinations), customizable progesterone preparations, and testosterone or DHEA additions when clinically indicated. Prescribers who understand the full toolkit can pivot quickly when one product becomes unavailable.

Establish your compounding partner before you need one. The worst time to vet a compounding pharmacy is when your patient is mid-shortage and needs a prescription filled tomorrow. Identify a PCAB-accredited pharmacy now—verify their HRT compounding volume, confirm potency testing protocols, and set up your prescribing workflow. Digital platforms like eNavvi make this particularly efficient: browse HRT formulation templates, compare pricing across pharmacies, and send electronic prescriptions without phone calls or faxes.

Counsel patients on the difference between compounding and unregulated products. Shortages drive patients to search for alternatives on their own—including online hormone products, over-the-counter "bioidentical" creams, and unverified supplements. Prescribers have an obligation to explain that physician-prescribed, pharmacy-compounded HRT from an accredited pharmacy is fundamentally different from self-directed purchases of unregulated products. The compounding pathway preserves clinical oversight. The internet pathway does not.

Give Your Patients HRT Options—Even During Shortages

Browse eNavvi’s compounded HRT templates—Bi-Est creams, micronized progesterone, testosterone, and DHEA—with transparent cash pricing across PCAB-accredited pharmacies. Free for prescribers. Your patients shouldn’t have to wait for a supply chain to catch up.

Frequently Asked Questions

Q: Why are estrogen patches in short supply in 2026?

A: The estrogen transdermal patch shortage is driven by a combination of surging demand (HRT prescriptions for women are up 86% since 2021), manufacturer consolidation (only three companies produce the majority of U.S. estradiol patches after Bayer discontinued Climara in 2023), the FDA’s removal of boxed warnings on HRT products (which accelerated prescribing), and tariff pressures on overseas pharmaceutical manufacturing. The shortage is affecting major pharmacy chains nationally.

Q: Is compounded estrogen safe?

A: Compounded estrogen preparations use the same bioidentical hormones (estradiol, estriol) found in FDA-approved products, but they are custom-prepared by compounding pharmacies and are not FDA-approved. Quality can vary between pharmacies, which is why pharmacy selection matters. PCAB-accredited compounding pharmacies are held to rigorous standards for potency testing, ingredient sourcing, and compounding consistency. Prescribers should use compounded HRT when FDA-approved products are unavailable or clinically insufficient, and should always route orders to accredited pharmacies.

Q: What alternatives exist if my patient can’t get estradiol patches?

A: Alternatives to estradiol patches include FDA-approved transdermal gels and sprays, oral estradiol (with a different clot-risk profile), vaginal estrogen preparations for genitourinary symptoms, and compounded transdermal estradiol creams from PCAB-accredited pharmacies. Compounded options offer the advantage of customizable dosing and the same transdermal delivery route as patches, maintaining therapeutic continuity for patients who prefer to avoid oral formulations. Prescribers can compare options and pricing on platforms like eNavvi.


Read More
AAD 2026: The Compounding Conversations Every Dermatology Prescriber Should Be Having

As thousands of dermatologists, residents, and prescribers gather in Denver for the American Academy of Dermatology’s 2026 Annual Meeting, the scientific sessions will cover the usual spectrum: biologics for atopic dermatitis, checkpoint inhibitor dermatology, advances in melanoma imaging, new approaches to acne scarring. What won’t get its own plenary session—but will be discussed in hallways, exhibit halls, and dinners across the city—is the rapidly evolving role of compounding in dermatology practice.

Three developments are converging to make 2026 a pivotal year for dermatology compounding: the FDA’s peptide reclassification is restoring access to key molecules used in skin and wound healing, tightening quality standards are separating accredited pharmacies from the rest, and digital prescribing platforms are finally eliminating the operational friction that has kept many dermatologists from incorporating compounding into their standard workflow.

Whether you’re already prescribing compounded topicals or considering it for the first time, here’s what’s shaping dermatology compounding right now—and what to bring back to your practice after AAD.

The Peptide Reclassification: What It Means for Dermatology

The biggest regulatory shift affecting dermatology compounding in 2026 isn’t about topical steroids or retinoids—it’s about peptides. On February 27, HHS announced that approximately 14 of the 19 peptides placed on the FDA’s Category 2 restricted list in late 2023 are expected to be moved back to Category 1, restoring legal access through licensed compounding pharmacies.

Two of those peptides are directly relevant to dermatology practice.

GHK-Cu (copper peptide). GHK-Cu is one of the most studied peptides in skin biology. It occurs naturally in human plasma and declines with age. Research has investigated its role in skin remodeling, collagen synthesis, wound healing, and antioxidant enzyme activity. Before the Category 2 restriction, GHK-Cu was a staple in compounded anti-aging and post-procedure formulations—used topically in serums and creams for photoaging, surgical wound recovery, and overall skin rejuvenation. Its expected return to Category 1 reopens a formulation pathway that dermatology compounders have been unable to offer for over two years.

KPV. Derived from alpha-melanocyte-stimulating hormone (alpha-MSH), KPV has been studied for anti-inflammatory properties relevant to both dermatology and gastroenterology. In skin applications, KPV’s anti-inflammatory mechanism has been explored for conditions involving cutaneous inflammation. While the evidence base remains early-stage, the peptide’s reclassification gives dermatology prescribers an additional compounding option for patients with inflammatory skin conditions that have been inadequately controlled by conventional therapies.

BPC-157. Although primarily associated with musculoskeletal repair, BPC-157’s wound-healing properties have dermatology relevance. Research has investigated its effects on tissue repair, angiogenesis, and collagen formation—mechanisms that intersect with wound care, post-surgical healing, and chronic skin ulcer management. Its expected reclassification may expand the compounding toolkit for prescribers who manage complex wound care cases.

The critical caveat: the formal FDA reclassification has been announced but not yet published in the Federal Register as of mid-March 2026. Until it’s official, these peptides cannot be legally compounded. Prescribers should monitor the FDA’s bulk drug substances list for the formal update before ordering.

Compounded Formulations Gaining Traction in Dermatology

Beyond peptides, several categories of compounded dermatology formulations are seeing increased prescriber interest heading into AAD 2026. These reflect both clinical demand and the limitations of what commercial products currently offer.

High-concentration minoxidil combinations for alopecia. Commercial minoxidil tops out at 5% (topical) and 2% (for women). Compounding pharmacies can prepare minoxidil at concentrations up to 12.5%, and—critically—combine it with topical finasteride (0.1–0.25%) and latanoprost (0.005%) in a single scalp solution. This multi-agent approach, increasingly supported by dermatology literature, is only possible through compounding. For prescribers who treat androgenetic alopecia aggressively, this remains one of the strongest clinical cases for compounding in dermatology.

Customized melasma protocols. The modified Kligman’s formula—combining hydroquinone, tretinoin, and a corticosteroid—has been a dermatology compounding staple for decades. But the compounding advantage goes beyond the standard formula. Prescribers can adjust hydroquinone beyond the commercial 4% ceiling (up to 8% for refractory cases), swap the steroid component based on patient sensitivity, add tranexamic acid or cysteamine for resistant pigmentation, and choose vehicle bases optimized for different skin types and climates. With melasma management increasingly moving toward individualized protocols, compounding gives prescribers the formulation flexibility that fixed commercial products cannot.

Combination acne formulations. Commercial acne products offer two or three fixed-dose combinations. Compounding opens the full matrix: tretinoin at any strength (0.025–0.1%) paired with clindamycin, niacinamide (4–5% for barrier support), azelaic acid, or dapsone—in a vehicle selected for the patient’s skin type. For adult acne patients who have cycled through commercial options, or patients with sensitivities to commercial vehicle ingredients, compounded formulations provide a next step that doesn’t require jumping to systemic therapy.

Post-procedure and wound healing compounds. The post-procedure recovery market is growing alongside the expansion of in-office aesthetic procedures. Compounded preparations combining antimicrobial agents, anti-inflammatory ingredients, and healing promoters—tailored to the specific procedure (chemical peel, laser resurfacing, microneedling, excisional surgery)—allow prescribers to optimize wound healing rather than relying on generic over-the-counter recovery products. The potential return of GHK-Cu to compounding adds another evidence-backed ingredient to this formulation category.

The Quality Question: Why Accreditation Matters for Dermatology Compounds

If there’s one topic that should concern every dermatologist who prescribes compounded medications, it’s potency consistency. The National Academies of Sciences, Engineering, and Medicine documented potency deviations in compounded hormone preparations as high as 26% from the labeled amount. For dermatology compounds, the stakes are similar: a hydroquinone cream compounded at 6% that actually contains 4.2% will deliver a meaningfully different clinical result. A tretinoin preparation with inconsistent distribution in the cream base will produce uneven results across the application area.

This is why pharmacy accreditation matters more in dermatology compounding than many prescribers realize. PCAB-accredited pharmacies—only about 8% of U.S. pharmacies hold this designation—are held to documented standards for potency testing, ingredient sourcing from FDA-registered suppliers, staff competency, and compliance with USP ⟨795⟩ (non-sterile) and ⟨797⟩ (sterile) compounding standards. For prescribers writing complex multi-ingredient topical formulations, the difference between an accredited pharmacy and a non-accredited one is the difference between a verified formulation and a best guess.

The February 2026 strategic alliance between eNavvi and ACHC (the Accreditation Commission for Health Care, which administers PCAB accreditation) was designed specifically to address this quality gap. Every compounding pharmacy in eNavvi’s network holds PCAB or equivalent accreditation, and the ACHC alliance provides member pharmacies with a direct pathway to achieve and maintain that accreditation—including reduced accreditation fees and access to ACHC’s educational resources.

The Digital Prescribing Shift: Why Workflow Matters as Much as Formulation

Ask any dermatologist why they don’t prescribe compounded medications more often, and the answer is rarely clinical. It’s operational. Calling a compounding pharmacy to discuss formulation details. Faxing a handwritten order. Not knowing the price until the patient is called by the pharmacy. Maintaining separate accounts with different pharmacies. The friction isn’t in the medicine—it’s in the workflow.

Digital prescribing platforms designed for compounding are eliminating these barriers. eNavvi’s platform gives dermatology prescribers access to pre-formulated templates for the most commonly prescribed compounds—melasma combinations, alopecia formulations, anti-aging preparations, wound care compounds—that can be customized within the digital workflow. Adjust concentrations, change the vehicle base, add or remove ingredients, and see real-time cash pricing from multiple PCAB-accredited pharmacies side by side before sending the prescription electronically.

For a dermatology practice that currently prescribes even a handful of compounded medications per week, replacing phone calls and faxes with a single digital interface reclaims meaningful clinical time. For practices that have avoided compounding because of the operational overhead, the barrier to entry has never been lower.

What to Bring Back from Denver

AAD 2026 will deliver cutting-edge science across every dermatology subspecialty. But some of the most practical takeaways won’t come from the podium. They’ll come from asking the right questions in the exhibit hall, connecting with compounding pharmacy partners, and returning to practice with a plan to integrate compounding into your clinical workflow more effectively.

Three action items to consider:

Identify your top 3–5 formulations. Look at your prescribing patterns and identify the clinical scenarios where commercial products fall short—whether it’s a melasma patient who has failed standard Kligman’s, an alopecia patient who would benefit from combination minoxidil-finasteride, or a post-procedure protocol you’d like to standardize. Start with these formulations rather than trying to build a comprehensive compounding program overnight.

Vet your compounding partner now. Before you return from Denver, decide which compounding pharmacy you’ll work with. Check for PCAB accreditation, ask about dermatology-specific compounding volume and experience, verify ingredient sourcing, and confirm potency testing protocols. A digital prescribing platform like eNavvi simplifies this: every pharmacy in the network is already accredited and vetted.

Watch the peptide timeline. The formal FDA reclassification of GHK-Cu, KPV, and other dermatology-relevant peptides hasn’t been published yet. When it is, having an accredited compounding partner already in place means you can begin incorporating these peptides into your practice immediately—rather than scrambling to find a pharmacy after the fact.

At AAD? Start Your Compounding Workflow Before You Leave Denver

Explore eNavvi’s dermatology compound templates—melasma, alopecia, acne, wound care, anti-aging—with transparent cash pricing across PCAB-accredited pharmacies. Free for prescribers. No phone calls, no faxes, no separate pharmacy portals.

Frequently Asked Questions

Q: What compounded medications are most commonly prescribed in dermatology?

A: The most commonly compounded dermatology medications include custom-strength hydroquinone and modified Kligman’s formulas for melasma and hyperpigmentation, high-concentration minoxidil (5–12.5%) combined with topical finasteride for alopecia, retinoid-antibiotic combinations for acne, steroid-keratolytic combinations for psoriasis and eczema, and multi-agent wound care and post-procedure preparations. Compounding allows prescribers to customize concentrations, combine multiple active ingredients, and select vehicle bases tailored to each patient’s skin type and condition.

Q: Are GHK-Cu and other peptides available for dermatology compounding in 2026?

A: As of March 2026, GHK-Cu and other peptides previously on the FDA’s Category 2 restricted list are expected to be reclassified to Category 1, which would restore legal access through licensed compounding pharmacies. The HHS announcement was made on February 27, 2026, but the formal reclassification has not yet been published in the Federal Register. Until the official update, these peptides cannot be legally compounded. Prescribers should monitor the FDA’s bulk drug substances list for the formal rule publication.

Q: How do I start prescribing compounded dermatology formulations?

A: Start by identifying the clinical scenarios in your practice where commercial products fall short. Select a PCAB-accredited compounding pharmacy (only ~8% of U.S. pharmacies hold this accreditation) or use a digital prescribing platform like eNavvi that connects prescribers exclusively to accredited pharmacies. You can browse pre-formulated dermatology templates, customize formulations, compare transparent cash pricing, and send prescriptions electronically—eliminating the phone calls and faxes that have historically made compounding operationally difficult for dermatology practices.


Read More
FDA Peptide Reclassification 2026: What Every Prescriber Needs to Know

On February 27, 2026, HHS Secretary Robert F. Kennedy Jr. announced that approximately 14 of the 19 peptides previously placed on the FDA’s Category 2 restricted list are expected to be moved back to Category 1—restoring legal access through licensed compounding pharmacies under a physician’s prescription.

For prescribers who incorporate peptide therapy into their clinical practice—across specialties from regenerative medicine and integrative health to endocrinology and sports medicine—this is the most consequential regulatory development in peptide compounding since the original restrictions were imposed in late 2023. But the announcement comes with critical nuances that every prescriber needs to understand before writing a single order.

What Happened: The Category 2 Restriction and Its Impact

In late 2023, the FDA placed 19 widely used peptides on its Category 2 bulk drug substances list. Category 2 designation means the FDA identified these substances as presenting potential safety concerns and deemed them not currently eligible for routine compounding under Sections 503A or 503B of the Federal Food, Drug, and Cosmetic Act.

The practical effect was immediate and sweeping. Licensed compounding pharmacies that had been preparing these peptides for years—under physician prescriptions, with quality controls and potency testing—were required to stop. The 19 restricted peptides spanned nearly every major clinical category in peptide therapy: tissue repair (BPC-157, Thymosin Beta-4), immune modulation (Thymosin Alpha-1, Selank), growth hormone signaling (CJC-1295, Ipamorelin, GHRP-2, GHRP-6), metabolic support (AOD-9604, MOTS-C), cognitive health (Semax, Selank), wound healing (GHK-Cu), and others including KPV, Kisspeptin-10, Melanotan II, PEG-MGF, Epitalon, Cathelicidin LL-37, and Emideltide (DSIP).

For prescribers, the restriction created an immediate clinical gap. Patients who had been on stable, physician-supervised peptide regimens lost access to compounds that had no FDA-approved equivalent. The restrictions also pushed some patients toward unregulated sources—research-grade peptides, overseas suppliers, and gray-market vendors—creating precisely the safety concerns the FDA’s action was intended to prevent.

What’s Changing: The Reclassification to Category 1

The HHS announcement signals that approximately 14 of the 19 restricted peptides will be reclassified from Category 2 to Category 1. Category 1 status means these substances are eligible for compounding by licensed pharmacies under a valid physician prescription—the same regulatory framework that governs compounded HRT, dermatology preparations, and other compounded medications.

Peptides that have already been removed from Category 2 and referred to the Pharmacy Compounding Advisory Committee (PCAC) for formal review include CJC-1295, Ipamorelin, Thymosin Alpha-1, AOD-9604, and Selank. Others with favorable early clinical profiles—including BPC-157, GHK-Cu, KPV, MOTS-C, Semax, and Thymosin Beta-4 fragment—are expected to follow.

Approximately five peptides are expected to remain on Category 2 due to more serious safety concerns or insufficient human evidence. As of this writing, the formal FDA reclassification has been announced but not yet officially published in the Federal Register. Until the FDA formally updates the Category 2 list, the legal status of these peptides for compounding remains technically unchanged.

Critical distinction for prescribers: Category 1 reclassification does not mean FDA approval. These remain off-label therapeutics. There are no FDA-approved peptide drugs for most of the clinical applications prescribers use them for. Reclassification simply restores the legal pathway for licensed compounding pharmacies to prepare them under physician prescription—with all the clinical oversight, dosing responsibility, and monitoring obligations that entails.

What This Means for Prescribers: Peptides by Clinical Category

The peptides expected to return span five broad clinical categories. Here’s what prescribers in each area should know.

Tissue Repair and Musculoskeletal Recovery. BPC-157 and Thymosin Beta-4 (TB-500) are among the most widely prescribed peptides in regenerative and sports medicine. BPC-157 has been studied for gut healing, tendon and ligament repair, and anti-inflammatory effects. Thymosin Beta-4 has been investigated for wound healing and tissue repair. For prescribers in orthopedics, sports medicine, and integrative health, the return of these peptides restores a therapeutic toolkit that has been unavailable for over two years. Clinical oversight remains essential: dosing protocols, treatment duration, and patient monitoring should follow established peptide therapy guidelines.

Immune Modulation. Thymosin Alpha-1 has the strongest clinical evidence base of any peptide on the list, with published research in infectious disease support, immune reconstitution, and oncology-adjacent immune modulation. It was used clinically in over 35 countries before the FDA’s Category 2 restriction. Selank, studied for its anxiolytic and immunomodulatory properties, is also expected to return. For prescribers in functional medicine and immunology, these peptides fill a gap that no FDA-approved product currently addresses.

Growth Hormone Signaling and Metabolic Support. CJC-1295 and Ipamorelin—often prescribed in combination—are growth hormone-releasing peptides used to support sleep quality, lean body composition, metabolic health, and recovery. AOD-9604, a modified fragment of human growth hormone, has been studied for its effects on fat metabolism without the broader growth hormone effects. MOTS-C, a mitochondrial-derived peptide, has been investigated for metabolic regulation and exercise performance. These peptides serve a prescriber population in anti-aging medicine, endocrinology, and metabolic health that had limited alternatives during the restriction period.

Cognitive Health and Neuroprotection. Semax, a synthetic peptide derived from ACTH, has been studied for cognitive enhancement, neuroprotection, and attention support. Selank overlaps here as well, with research into its effects on anxiety and cognitive function. For prescribers in neurology and cognitive health, the reclassification reopens access to peptides that were previously part of established treatment protocols for select patients.

Skin and Wound Healing. GHK-Cu (copper peptide) is one of the most studied peptides for skin remodeling, wound healing, and anti-aging applications. KPV, derived from alpha-melanocyte-stimulating hormone, has been studied for its anti-inflammatory properties in skin and gut conditions. For prescribers in dermatology and aesthetic medicine, these peptides expand the compounded formulation toolkit alongside established topical compounds.

The Compliance Imperative: Why Pharmacy Selection Matters More Than Ever

The return of compounded peptides to legal status amplifies—rather than diminishes—the importance of pharmacy quality and regulatory compliance. Here’s why.

Sourcing verification is critical. Peptides are complex molecules that require verified sourcing from FDA-registered API suppliers, certificates of analysis for identity and purity, and proper cold-chain handling. During the restriction period, gray-market peptide vendors proliferated—many without any of these safeguards. As peptides return to licensed compounding, prescribers must ensure they’re ordering from pharmacies that can document their entire supply chain, not pharmacies that pivot to peptides opportunistically without the infrastructure to handle them safely.

Potency and sterility testing are non-negotiable. Injectable peptides demand the highest compounding standards: sterile technique, potency verification, endotoxin testing, and stability data. PCAB-accredited pharmacies are held to these standards through documented protocols, on-site inspections, and compliance with USP ⟨797⟩ for sterile compounding. For peptides—where dosing is measured in micrograms and administration is typically subcutaneous injection—compounding quality directly determines clinical safety.

Off-label prescribing requires clinical discipline. Category 1 reclassification does not create an evidence base that didn’t exist before. These peptides remain investigational for most applications. Responsible prescribing means proper patient selection, evidence-informed dosing, baseline and follow-up lab monitoring where appropriate, documented informed consent, and clinical follow-up to assess response. The regulatory landscape is shifting. The need for physician-guided, compliance-first prescribing is not.

Read More
Compounded Dermatology Medications: What Prescribers Need to Know

Dermatology has one of the strongest clinical cases for compounding. Patients present with conditions that demand specific concentrations, unique ingredient combinations, or vehicles that commercial products simply don’t offer. A patient who needs a higher-strength tretinoin than what’s commercially available. A combination antifungal-steroid-antibiotic in a single topical. A hydroquinone preparation without a specific preservative that triggers contact dermatitis. These are everyday clinical scenarios in dermatology—and compounding addresses them.

Yet many prescribers default to commercial alternatives or avoid compounding entirely because the ordering workflow is cumbersome, quality is uncertain, or they’re unsure what’s available. This guide covers the clinical landscape of compounded dermatology medications—common formulations, quality considerations, and how digital prescribing tools are making dermatology compounding more accessible.

When Compounded Dermatology Formulations Are Clinically Indicated

FDA-approved dermatology products cover a wide therapeutic range, and they should be the starting point when they meet the patient’s needs. Compounding becomes relevant in specific clinical circumstances:

Custom concentration requirements. A patient may need a strength that isn’t commercially available—a higher or lower concentration of a retinoid, a non-standard percentage of hydroquinone, or a steroid potency between two available commercial products. Compounding allows precise strength adjustments.

Multi-agent combination therapy. Dermatology frequently benefits from combining multiple active ingredients into a single preparation. A melasma formulation combining hydroquinone, tretinoin, and a corticosteroid. A wound care compound with an antimicrobial, analgesic, and healing agent. Commercial products rarely offer these combinations, and applying three separate products creates compliance challenges for patients.

Allergen or excipient avoidance. Patients with contact sensitivities to preservatives, fragrances, dyes, or specific vehicle ingredients may react to a commercial product’s inactive ingredients. Compounding allows the active drug to be delivered in a hypoallergenic base free of the offending excipient.

Vehicle optimization. The vehicle matters in dermatology. An ointment base for severely dry plaques, a gel for seborrheic areas, a foam for scalp application, a cream for cosmetically sensitive areas. Compounding lets the prescriber match the vehicle to the body site and skin condition rather than accepting whatever vehicle the manufacturer chose.

Common Compounded Dermatology Formulations

The following formulations represent the most frequently compounded dermatology preparations. Concentrations reflect common prescribing ranges; individual clinical judgment should always guide specific prescribing decisions.

Hyperpigmentation and Melasma. The modified Kligman’s triple combination cream remains one of the most widely prescribed compounded dermatology formulations. A typical preparation combines hydroquinone (4–8%), tretinoin (0.025–0.05%), and fluocinolone acetonide (0.01%) in a single topical cream. Compounding allows prescribers to adjust the hydroquinone concentration beyond the 4% ceiling of most commercial products and to customize the vehicle for patient tolerance.

Acne. Custom retinoid and antibiotic combinations give prescribers flexibility that commercial fixed-dose products cannot match. Common formulations include tretinoin (0.025–0.1%) paired with clindamycin (1%) and niacinamide (4–5%). Compounding allows the prescriber to fine-tune retinoid strength based on patient tolerance and to add agents like niacinamide for barrier support—combinations not available in any single commercial product.

Anti-Aging and Photoaging. High-strength retinoid and antioxidant creams are among the most requested compounded preparations in cosmetic dermatology. Formulations typically feature tretinoin (0.05–0.1%) combined with vitamin C (10–20%) and hyaluronic acid in a cosmetically elegant base. Compounding allows concentrations of vitamin C and retinoid that exceed what’s available in over-the-counter or prescription commercial products.

Fungal Infections. Multi-agent antifungal topicals combine two or more antifungal agents—such as ketoconazole (2%) and clotrimazole (1%)—sometimes with a low-potency corticosteroid to manage inflammation. This approach is particularly useful for refractory dermatophyte infections or mixed fungal-inflammatory presentations where a single commercial antifungal has proven insufficient.

Psoriasis and Eczema. Steroid and keratolytic combinations address both inflammation and hyperkeratosis in a single application. Common formulations pair betamethasone (0.05–0.1%) with salicylic acid (3–6%) and calcipotriene (0.005%). Compounding allows the prescriber to adjust steroid potency by body site—lower for face and flexures, higher for thick plaques on elbows and knees—in a way that fixed commercial products cannot accommodate.

Wound Care. Antimicrobial and healing agent preparations combine ingredients like mupirocin (2%) with agents that promote tissue repair—misoprostol, phenytoin, or nifedipine—tailored to the wound type and healing stage. These multi-agent compounds are used in chronic wound management, post-surgical care, and pressure injury treatment where commercial wound care products offer insufficient therapeutic breadth.

Scar Management. Silicone-based preparations with active ingredients offer a compounded alternative to commercial scar sheets and gels. Formulations may combine a silicone base with vitamin E, onion extract, and a low-potency corticosteroid. Compounding allows the prescriber to adjust the active ingredient profile based on scar type (hypertrophic, keloid, post-surgical) and patient response.

Alopecia. Scalp-targeted formulations represent a growing area of compounding interest. Common preparations include minoxidil at higher concentrations than commercially available (5–12.5%), often combined with topical finasteride (0.1–0.25%) and latanoprost (0.005%) in a single scalp solution. Compounding is the only way to deliver these multi-agent combinations in a single application.

Nail Conditions. Nail-penetrating antifungal formulations use specialized vehicles—often DMSO-based—to deliver antifungal agents like ciclopirox and terbinafine through the nail plate. Onychomycosis is notoriously difficult to treat topically with commercial products; compounded formulations with enhanced penetration vehicles offer an alternative for patients who cannot tolerate or prefer to avoid systemic antifungals.

Note: Compounded preparations are not FDA-approved. Prescribers should document the clinical rationale for compounding, explain to patients that the formulation is custom-prepared, and select accredited compounding pharmacies to minimize quality variability.

Quality Matters More in Dermatology Than You Think

Topical compounding quality directly affects therapeutic outcomes. Potency accuracy determines whether the active ingredient is delivered at the intended concentration. Vehicle stability determines whether the active remains evenly distributed and bioavailable throughout the preparation’s shelf life. Beyond-use dating (BUD) determines how long the compound remains clinically effective.

Studies have documented significant potency variability in compounded preparations across pharmacies. For topical dermatology compounds—where a 4% hydroquinone cream that tests at 2.8% delivers a meaningfully different clinical effect—this variability has real patient-care implications.

PCAB-accredited pharmacies are held to rigorous standards for compounding consistency, potency verification, and ingredient sourcing from FDA-registered suppliers. For dermatology prescribers who send compound orders regularly, routing those orders exclusively to accredited pharmacies is the simplest way to control for quality variability.

How to Order Compounded Dermatology Medications Digitally

Historically, prescribing a compounded dermatological preparation meant calling a specific pharmacy, discussing the formulation details, and faxing a written order. Digital prescribing platforms designed for compounding eliminate this friction.

eNavvi’s platform provides access to pre-formulated dermatology templates for the most commonly prescribed compounds—including melasma combinations, high-strength retinoids, and custom alopecia formulations. Each template is fully customizable: adjust concentrations, change the vehicle base, add or remove ingredients, and modify quantities within the digital workflow. Real-time cash pricing from multiple PCAB-accredited pharmacies is displayed side by side, so prescribers can compare costs before finalizing the order.

For dermatology practices that prescribe compounds regularly, this workflow replaces dozens of phone calls and faxes per week with a single digital interface—complete with audit trails, HIPAA-secure transmission, and documented formulation records for each patient.

Browse Dermatology Compound Templates

Explore eNavvi’s pre-formulated dermatology compounds—melasma, acne, alopecia, wound care, and more—with transparent cash pricing across PCAB-accredited pharmacies.

Get Started Free at eNavvi.com →

Frequently Asked Questions

Q: What dermatology medications can be compounded?

A: Nearly any topical dermatology medication can be compounded, including retinoids (tretinoin), hydroquinone, antifungals (ketoconazole, terbinafine), corticosteroids, antibiotics (clindamycin, mupirocin), minoxidil for alopecia, and multi-agent combinations. Compounding allows custom concentrations, allergen-free bases, and combination formulations that are not commercially available.

Q: Are compounded dermatology medications covered by insurance?

A: Most compounded dermatology medications are cash-pay and are not covered by insurance. Because they are custom-prepared without FDA approval, insurance plans and PBMs typically do not adjudicate claims for compounded topicals. This makes transparent cash pricing especially important—platforms like eNavvi display real-time prices from multiple pharmacies so prescribers and patients can compare costs before the order is placed.

Q: How do I choose a compounding pharmacy for dermatology prescriptions?

A: Look for PCAB accreditation (only ~8% of U.S. pharmacies hold this), verify they compound dermatology formulations regularly (volume indicates process consistency), confirm ingredient sourcing from FDA-registered suppliers, and ask about potency testing protocols. Digital prescribing platforms like eNavvi include only accredited pharmacies in their network, simplifying the selection process.

Read More
A Prescriber’s Guide to Compounded HRT: Formulations, Dosing, and How to Order

Hormone replacement therapy compounding represents the single largest category in compounding pharmacy, accounting for approximately 36% of all compounding prescriptions nationally according to the Alliance for Pharmacy Compounding. For prescribers in family medicine, OB/GYN, endocrinology, and integrative medicine, compounded HRT fills a specific clinical need: providing hormone preparations in formulations, dosage forms, and strengths that FDA-approved products do not cover.

This guide walks through the clinical landscape of compounded HRT prescribing—from when compounding is clinically appropriate, to the formulations and dosage forms available, to how prescribers can select quality compounding partners and streamline the ordering process.

When Compounded HRT Is Clinically Appropriate

FDA-approved hormone therapy products should be the starting point for most patients. Dozens of FDA-approved estrogen, progesterone, and testosterone products are available in various strengths and delivery systems, and these products have undergone rigorous review for safety, efficacy, and manufacturing consistency. Both ACOG and the Endocrine Society recommend FDA-approved formulations as first-line therapy when they meet the patient’s clinical needs.

Compounded HRT becomes clinically relevant when FDA-approved options are insufficient for a specific patient’s situation. Common clinical scenarios include:

Allergy or sensitivity to inactive ingredients. A patient may react to a dye, preservative, filler, or adhesive in a commercial product. Compounding allows the formulation to exclude the specific allergen while delivering the same active ingredient.

Need for a non-standard strength. FDA-approved products come in fixed doses. Some patients require titration to a strength between commercially available options, or need a starting dose lower than the lowest commercial product offers. Compounding allows precise dose customization.

Preferred dosage form not commercially available. A patient may need a topical cream when only oral capsules are available in the needed hormone, or a sublingual preparation when they cannot tolerate oral delivery. Compounding expands the dosage-form options beyond what the commercial market provides.

Combination therapy in a single preparation. Some prescribers prefer to combine multiple hormones (e.g., estriol and estradiol, or estrogen with progesterone) into a single preparation to simplify the patient’s regimen. While evidence supporting specific multi-hormone combinations is limited, this approach is widely used in clinical practice when single-agent commercial products would require the patient to use multiple separate products.

Important clinical note: Prescribers should counsel patients that compounded preparations are not FDA-approved, that quality can vary between pharmacies, and that the evidence base for specific compounded formulations is more limited than for FDA-approved products. These are essential elements of informed consent when prescribing compounded HRT.

Read More

No valid Image was found

Continuous Glucose Monitoring (CGM) in 2025: A Practical, Cost-Conscious Prescribing Guide for Physicians

Executive summary

Continuous glucose monitoring (CGM) is now standard of care for many adults with diabetes, and 2025 brings clarifying guidance, simpler eligibility, and new device options. ADA Standards of Care 2025 support CGM across a broader clinical spectrum, while Medicare criteria now cover all insulin-treated patients and certain non-insulinpatients with documented problematic hypoglycemia. Recent device updates (e.g., Dexcom G7 “15-day” sensor clearance) further simplify use. A consistent, price-transparent workflow—compare costs, confirm coverage, e-prescribe—can reduce callbacks and improve adherence. Diabetes JournalsAmerican Diabetes AssociationAmerican Academy of Family PhysiciansCenters for Medicare & Medicaid ServicesDexCom Investors

1) Evidence & indications: who should be on CGM in 2025?

ADA 2025 recommends real-time (rtCGM) or intermittently scanned CGM (isCGM) to improve glycemic outcomes across age groups. The 2025 update also highlights CGM consideration for adults with type 2 diabetes on glucose-lowering agents beyond insulin when clinically appropriate. These recommendations reflect strong data for A1C reduction, hypoglycemia mitigation, and time-in-range improvements. Diabetes JournalsAmerican Diabetes Association

2) Coverage & access: what changed and how to operationalize it

Medicare: Coverage now includes (1) any insulin-treated beneficiary and (2) individuals with problematic hypoglycemia meeting documentation criteria, with the historical finger-stick requirement removed. Practically: document diagnosis, insulin use (if applicable), and/or specific hypoglycemia events; reference the local coverage article language in your note. American Academy of Family PhysiciansCenters for Medicare & Medicaid ServicesAmerican Diabetes Association

Commercial: Plans vary, but many mirror Medicare’s modernization. When insurance is prohibitive or delays care, offer transparent cash-pay options and let patients decide at the point of care. eNavvi’s platform is designed for side-by-side cash-price comparison and direct prescribing. enavvi.comformulary.enavvi.com

3) Device landscape & counseling pearls (2025)

  • Dexcom G7 (including 15-day): In April 2025, FDA cleared Dexcom G7 15-day for adults (anticipated U.S. availability in the second half of 2025). Discuss wear duration, accuracy, app ecosystem, and compatibility with AID systems as updates roll out. DexCom InvestorsDexcom
  • FreeStyle Libre 3: Ensure patients are on current lots; note prior 2024 sensor medical device correction affecting a small distribution window. Counsel on adhesive care and app usage. U.S. Food and Drug Administration
  • Special situations: The FDA has acknowledged expanding device labeling related to imaging workflows for certain CGMs; verify current device instructions before CT/MRI to avoid interruptions. Verywell Health

Patient counseling quick-hits: alarm fatigue mitigation, how to act on trends vs. single readings, sick-day rules, and when to confirm with capillary testing.

4) Coding & documentation you’ll actually use

  • Technical/Setup & Training: 95249 (personal CGM) or 95250 (professional CGM placement/training), typically once per 30 days as applicable.
  • Interpretation/Report: 95251 (CGM analysis/interpretation/report).
  • Remote monitoring (when used): pair with RPM codes per payer policy.
    Check your local payer policies for bundling/exclusions and POS rules. American Academy of Family Physiciansprovider.dexcom.com

5) A practical, point-of-care workflow (using eNavvi)

Search & compare: In eNavvi, look up CGM devices and compare cash prices vs likely coverage—so patients see their options up front. formulary.enavvi.com

Document eligibility: For Medicare, explicitly note insulin therapy or problematic hypoglycemia with qualifying events; for commercial plans, mirror criteria and include A1C/hypoglycemia history. Centers for Medicare & Medicaid Services

Counsel & consent: Review device specifics, app setup, data-sharing, and alert thresholds; set expectations for time-in-range goals. Diabetes Journals

E-prescribe: Send the device, sensors, and (if needed) reader via eNavvi for pickup or mail-order fulfillment to reduce friction and delays. enavvi.com

Follow-up: Schedule data review (2–4 weeks for initiation, then quarterly). Bill interpretation when appropriate (e.g., 95251). American Academy of Family Physicians

6) Safety alerts & special situations

  • Lot-specific issues: Libre 3 had a limited 2024 sensor correction; advise patients to contact support if readings seem inconsistent or if sensor is from the impacted period. U.S. Food and Drug Administration
  • Imaging: Confirm current labeling before CT/MRI; growing clearances reduce unnecessary removals but still verify per device. Verywell Health

Key takeaways

Read More
Digital Compounding Prescriptions in 2025: What Physicians Need to Know About Access, Safety, and Cost Transparency

Executive summary

Compounded medications continue to play an important role in patient care when FDA-approved products are unavailable, contraindicated, or insufficient for individualized needs. Yet variability in quality, oversight, and pricing creates risk for both patients and physicians. In 2025, digital prescribing platforms offer new opportunities for safer, compliant, and transparent access to compounded therapies.

1) What counts as compounding in 2025?

Compounding is defined as the preparation of a medication to meet the unique needs of a patient that cannot be met with an FDA-approved drug. This occurs under two main pathways: 503A traditional compounding pharmacies, which produce patient-specific prescriptions, and 503B outsourcing facilities, which compound in bulk under cGMP standards.

2) Why physicians prescribe compounded drugs

  • Patient-specific formulations: Alternative strengths, routes (e.g., rectal suppositories for GI indications), or dosage forms.
  • Allergy avoidance: Removal of excipients, dyes, or allergens.
  • Therapy gaps: When FDA-approved options are unavailable or discontinued.
  • Shortage mitigation: Temporarily filling access gaps.

3) Compliance & liability considerations

Physicians should prescribe only through accredited, reputable pharmacies. PCAB accreditation signals adherence to USP standards. Documentation of medical necessity is recommended, and physicians should avoid writing for compounded versions of drugs with readily available FDA-approved alternatives unless justified.

4) Cost transparency & patient trust

Pricing for compounded medications is notoriously opaque and varies widely by pharmacy. Digital platforms that show comparative pricing at the point of prescribing reduce sticker shock, increase adherence, and enhance patient trust. eNavvi, for example, integrates a compounding network that allows physicians to compare cash prices across PCAB-accredited pharmacies before finalizing the prescription.

5) Case examples

  • Dermatology: Customized topical creams (multi-agent formulations not commercially available).
  • GI: Rectal mesalamine suppositories for IBD patients intolerant to commercial formulations.
  • HRT: Bioidentical hormone replacement, where individualized dosing is required.

6) Streamlined prescribing workflow

Search and select compounded therapy (formulation, dosage form).

Compare accredited pharmacies and cash pricing.

Document indication and rationale (especially when FDA alternatives exist).

Route digitally to the pharmacy, minimizing fax/phone steps.

Track and follow up for adherence, AE reporting, and adjustments.

Key takeaways

  • Compounded medications remain clinically essential in select scenarios but pose compliance and liability risks.
  • Accreditation and documentation are key to mitigating risk.
  • Transparent digital prescribing tools improve trust, adherence, and outcomes.
Read More
Eflornithine HCl 13.9% Cream: Your High‑Precision Solution for Unwanted Facial Hair

Unwanted facial hair can be more than a cosmetic nuisance—it can affect confidence, daily routines, and quality of life. Eflornithine HCl 13.9% cream, available for fast digital prescribing through eNavvi, offers a clinically proven, prescription‑strength way to slow hair growth and extend the smooth interval between hair‑removal sessions.

What Is Eflornithine HCl 13.9% Cream?

Eflornithine is a topical medication formulated at 13.9% strength. Unlike depilatories that dissolve hair shafts or lasers that target follicles with heat, eflornithine works inside the follicle to reduce the rate and coarseness of new hair growth—making it an ideal adjunct to shaving, waxing, threading, or laser therapy.

Fast Facts

Attribute

Details

Active ingredient: Eflornithine hydrochloride monohydrate 13.9%

Presentation: 30‑gram tube (≈ 30‑day supply)

Price: $55

Shipping: 2‑day shipping via eNavvi partner pharmacy

Frequency: Apply twice daily, at least 8 hours apart

Onset of benefit: Visible slowing of growth in 4‑8 weeks (max 6 months)

FDA status: Prescription‑only (Rx)

How Does Eflornithine Work?

Mechanism of Action

Hair shafts grow when follicles produce the structural protein keratin, a process that relies on polyamines—small molecules synthesized by the enzyme ornithine decarboxylase (ODC). Topical eflornithine is a selective, irreversible ODC inhibitor:

Blocks polyamine synthesis inside the hair bulb.

Slows keratin assembly and cell division in the follicle matrix.

Extends the anagen (growth) phase, reducing the speed and thickness of emerging hair.

The result is finer, slower‑growing hair that requires less frequent removal. Because eflornithine does not destroy follicles, growth gradually returns to baseline about eight weeks after discontinuation.

Who Benefits Most?

Ideal Candidates

Women bothered by unwanted facial or submental hair (e.g., hirsutism, PCOS)

Patients seeking a non‑laser option for darker skin phototypes

Those using laser/IPL who want to extend treatment intervals

People experiencing irritation from frequent waxing or depilatories

eNavvi Tip: Dermatologists and primary‑care providers can digitally prescribe eflornithine in seconds, and patients receive it at their doorstep within two business days—no in‑person pharmacy trip required.

When Not to Use Eflornithine

  • Known hypersensitivity to eflornithine or cream excipients
  • Broken, inflamed, or infected skin in the application area
  • Children (< 12 years): safety not established
  • Pregnancy: Category C—use only if anticipated benefits outweigh potential fetal risk
  • Breastfeeding: Insufficient data; exercise caution and avoid application near the nipple area

Always discuss systemic conditions (e.g., severe acne, dermatitis), concurrent topical treatments (retinoids, benzoyl peroxide), and hair‑removal methods with your prescriber.

Dosage & Application Guide

Prep the skin: Remove hair by your usual method (shave, wax, etc.) and wait ≥ 5 min.

Clean & dry: Gently cleanse, pat dry.

Apply a thin film: Use pea‑sized dabs to cover only affected areas (avoid eyes, mouth, mucous membranes). Rub in until absorbed.

Frequency: 2× daily, morning & evening, at least 8 h apart.

Post‑application care: Avoid washing, swimming, or sweating heavily for 4 h after application.

Cosmetics: Makeup or sunscreen may be applied after the cream dries (~ 5 min).

If no clinical improvement is observed after 6 months, reassess therapy.

Expected Timeline

  • Weeks 0‑4: Subtle reduction in stubble feel; less five‑o‑clock shadow.
  • Weeks 4‑8: Noticeable slowdown in regrowth; hairs appear finer.
  • Months 3‑6: Peak effect; many users can shave/wax half as often.
  • > 6 months: Continue maintenance if satisfied; discontinue if inadequate response.

Stopping treatment leads to gradual return to baseline hair density within ~ 8 weeks.

Possible Side Effects

Most reactions are mild and limited to the skin surface:

  • Transient burning or stinging at application site
  • Redness, dryness, or itching
  • Acneiform eruptions or folliculitis
  • Tingling or rash
  • Contact dermatitis (rare)

Management tips: Use a gentle cleanser, avoid alcohol‑based toners, and apply non‑comedogenic moisturizer if needed. Discontinue and consult a clinician if severe irritation or allergic rash develops.

Systemic absorption is < 1%, so systemic side effects are exceedingly rare.

Best‑Practice Tips for Clinicians

  • Combine eflornithine with laser or IPL for synergistic results—slowing regrowth lets energy‑based treatments target fewer, slower‑cycling follicles.
  • Consider hormonal evaluation (androgen levels, PCOS work‑up) for women with rapid, coarse facial hair.
  • Document baseline photography; objective visuals help motivate adherence and gauge progress.
  • Remind patients that consistency is key—twice‑daily use is required for optimal suppression.

eNavvi Makes Prescribing Effortless

With eNavvi, you can:

Select Eflornithine HCl 13.9% cream

E‑sign the prescription in < 30 seconds.

Ship—our partner pharmacy delivers the 30‑g tube for $55 (2‑day shipping included).

Patients receive automated refill reminders, and you can track adherence and outcomes in your eNavvi dashboard—streamlining follow‑up care.

Key Takeaways

  • Topical eflornithine slows hair growth by inhibiting the ODC enzyme inside follicles.
  • Twice‑daily application delivers visible results in 4‑8 weeks; reassess at 6 months.
  • Common side effects are mild and local; systemic exposure is minimal.
  • Ideal for women with unwanted facial hair and a complement to laser or traditional hair‑removal methods.
  • eNavvi enables seamless prescribing and quick shipping, improving treatment initiation and adherence.

Ready to offer your patients a science‑backed solution for smoother skin? Log in to eNavvi, select Eflornithine HCl 13.9% cream, and make unwanted hair one less worry.

Disclaimer

This blog post is for informational purposes only and does not constitute medical advice. Patients should consult a licensed healthcare professional to determine whether eflornithine is appropriate for their individual needs.

Read More
Compounded Amitriptyline HCl/Lidocaine HCl/Pramoxine HCl 5/5/1% Cream: Pharmacological Insights and Clinical Applications in Pruritus Management

In the realm of dermatology and pain management, chronic pruritus remains a challenging symptom, often refractory to standard therapies and significantly impacting patient quality of life. For physicians seeking innovative, patient-specific interventions, compounded topical formulations offer a tailored approach. The amitriptyline HCl/lidocaine HCl/pramoxine HCl 5/5/1% cream represents a multimodal compounded agent designed for localized itch relief, particularly in neuropathic or mixed-etiology pruritus. Available through eNavvi's ePrescribing platform at $35 for a 30-gram tube (30-day supply) with 2-day shipping, this formulation combines sodium channel blockade, local anesthesia, and sensory nerve modulation to address the itch-scratch cycle effectively.

This article explores the pharmacology, evidence-based efficacy, prescribing considerations, and integration into clinical practice for this compounded cream, optimizing for searches related to "compounded topical pruritus treatment," "neuropathic itch management," and "amitriptyline lidocaine pramoxine cream."

Pharmacodynamics and Mechanism of Action

The synergistic components of this cream target peripheral neural pathways implicated in pruritus pathogenesis:

  • Amitriptyline HCl (5%): As a tricyclic antidepressant, amitriptyline inhibits voltage-gated sodium channels in peripheral nerves, reducing ectopic firing associated with neuropathic itch. Topical application minimizes systemic anticholinergic effects while providing analgesia comparable to local anesthetics. It is particularly efficacious in conditions involving nerve hypersensitivity, such as postherpetic neuralgia or brachioradial pruritus.
  • Lidocaine HCl (5%): A amide local anesthetic that stabilizes neuronal membranes by blocking sodium influx, thereby interrupting itch and pain signal transmission. Its rapid onset (within minutes) makes it ideal for acute symptom control in inflammatory or uremic pruritus.
  • Pramoxine HCl (1%): A non-amide anesthetic that desensitizes sensory nerve endings, offering antipruritic effects without the risk of amide cross-reactivity. Clinical data support its use in uremic and elderly pruritus, where it reduces itch intensity more effectively than vehicle controls.

This combination parallels ketamine-amitriptyline-lidocaine (KAL) formulations, which have demonstrated efficacy in chronic pruritus through retrospective analyses, with response rates of 50-70% in refractory cases. By substituting pramoxine for ketamine, this variant may reduce potential irritancy while maintaining multimodal blockade.

Clinical Indications and Evidence

Indicated for chronic pruritus of neuropathic, uremic, or idiopathic origin, this cream is suitable for conditions such as:

  • Brachioradial pruritus or prurigo nodularis, where nerve modulation is key.
  • Atopic dermatitis flares or psoriasis-associated itch, augmenting anti-inflammatory regimens.
  • Cancer-related or CKD-associated pruritus, as adjunctive therapy.

Retrospective studies on analogous compounded topicals (e.g., KAL) report significant itch reduction in 60% of patients with minimal adverse events, primarily transient erythema. Pramoxine-inclusive formulations have shown superior efficacy in hemodialysis patients, underscoring its role in uremic pruritus. While large-scale RCTs are limited for this exact combination, mechanistic overlap with validated agents supports its use in treatment-resistant cases.

Prescribing Guidelines and Safety Profile

Prescribe as a thin layer applied 2-4 times daily to intact skin, avoiding occlusion to prevent enhanced absorption. The 30-gram tube supports a 30-day course for localized areas.

Adverse Effects: Primarily local (e.g., transient stinging in 10-20% of users); systemic risks (e.g., sedation from amitriptyline) are rare with topical use but warrant monitoring in elderly or renally impaired patients.

Contraindications: Hypersensitivity to components; caution with concurrent antiarrhythmics or MAOIs due to potential interactions.

Monitoring: Assess response at 2 weeks; discontinue if irritation persists.

eNavvi facilitates seamless prescribing with real-time pricing transparency ($35/30g, 2-day shipping) and integration with networks like Mark Cuban Cost Plus Drug Company. As a physician-founded platform, it streamlines compounded medication orders, reducing administrative burden.

Integrating into Practice: A Cost-Effective Option

For physicians managing refractory pruritus, this cream offers a low-cost, accessible alternative to systemic therapies, aligning with guidelines emphasizing topical-first approaches. Leverage eNavvi for efficient ePrescribing and patient education on adherence.

In summary, amitriptyline HCl/lidocaine HCl/pramoxine HCl 5/5/1% cream provides a compelling option for pruritus management, backed by mechanistic rationale and supportive evidence from similar formulations. Explore prescribing via eNavvi to enhance patient outcomes.

Disclaimer: This content is for educational purposes and not a substitute for clinical judgment. Consult primary literature and patient-specific factors before prescribing.


Read More
Cutting‑Edge Compounded Options for Scar Management on eNavvi

Scars are not one-size-fits-all. From hypertrophic nodularity to post-inflammatory hyperpigmentation (PIH) and atrophic collagen loss, their presentations—and responses—vary. While over-the-counter silicone gels help some patients, many require targeted formulations to address pigmentation, erythema, and remodeling more precisely.

Compounded scar treatments from eNavvi offer:

  • Precision ingredients adjusted to patient phenotype, Fitzpatrick type, and healing stage
  • Silicone-plus vehicles (Pracasil® Plus) to enhance absorption while maintaining a moist, occlusive environment
  • Streamlined application through single-tube, multitarget formulations that improve adherence

All preparations are fulfilled by Foothills Professional Pharmacy, PCAB-accredited and licensed in all 50 states, with 2-day nationwide shipping and flat transparent pricing: $55 for a 30g, 30-day supply.

Key Compounded Scar Therapies Available on eNavvi

1. Hydroquinone 6% in Pracasil® Plus Base

This high-potency skin-lightening agent remains the gold standard for post-inflammatory hyperpigmentation. Compounded in a silicone-based gel, it provides dual-action benefit: hydroquinone reduces melanin synthesis via tyrosinase inhibition, while Pracasil® Plus softens and flattens scar tissue.

Clinical Use: Best for mature, pigmented scars—especially in Fitzpatrick III–VI skin after acne surgery, trauma, or lasers.

Prescribing Note: Apply a thin layer twice daily for up to 12 weeks; always pair with SPF 50+.

Caution: Contraindicated in pregnancy and breastfeeding. Limit continuous use to under 6 months to reduce risk of ochronosis.

2. Niacinamide 2% + Tretinoin 0.1% in Pracasil® Plus

This multitarget formula combines anti-inflammatory, barrier-restoring, and collagen-remodeling effects, making it ideal for early hypertrophic or mixed-type scars. Niacinamide reduces cytokine activity and transepidermal water loss, while tretinoin upregulates collagenase activity to encourage smoother remodeling.

Clinical Use: Begin 2 weeks post-procedure once epithelialized. Excellent for early surgical, ablative, or traumatic scars.

Prescribing Note: Apply a pea-sized amount nightly for 12–16 weeks. Titrate to every other night for sensitive skin.

Caution: Mild irritation and photosensitivity are expected—ensure patients use broad-spectrum sun protection.

3. Niacinamide 2% in Pracasil® Plus (Mono‑Active)

A minimalist yet effective option for sensitive skin or post-procedural cases unable to tolerate retinoids or hydroquinone. This formulation strengthens the skin barrier, reduces mast-cell-mediated inflammation, and soothes reactivity—making it suitable for both adult and pediatric patients.

Clinical Use: Ideal for postsurgical scars in pregnancy, pediatric dermatology, or rosacea-prone skin.

Prescribing Note: Apply twice daily for a minimum of 8 weeks. Often used as maintenance after more intensive therapies.

Caution: Safe across all skin types and life stages. No known contraindications.

How to Prescribe Scar Compounds via eNavvi

eNavvi’s workflow is designed for clinical speed and patient clarity:

Log in to your eNavvi account and select “Compounded eRx," then "Scar"

Choose your formulation—default SIG, volume, and quantity are preloaded.

E-sign the order and counsel your patient on application schedule and photoprotection.

Track healing via 4-week photographic intervals and adjust formulation or frequency as needed.

Clinical Data Snapshot

  • Pracasil® Plus base (silicone + pracaxi oil) achieved >38% improvement on the Vancouver Scar Scale in a 12-week prospective series.
  • Hydroquinone 6% improves PIH by 60–70% within 8–12 weeks in skin-of-color studies.
  • Tretinoin 0.1% promotes 21% increase in dermal collagen fiber organization after 6 months (histologically confirmed).
  • Niacinamide 2% improves barrier strength and reduces inflammation within 6 weeks in split-scar studies.

Key Takeaways for Dermatology Practices

  • Compounded scar gels allow personalized, phenotype-specific interventions across scar types and skin tones.
  • The Pracasil® Plus base enhances bioavailability while reducing irritation and occlusion-induced maceration.
  • All formulas are affordably priced at $55 and ship nationwide within 48 hours—supporting timely care across geographies.
  • This model supports high-acuity procedures, enhances adherence, and integrates seamlessly into post-op protocols.
Read More
  • Previous
  • 1(current)
  • Next